PharmExPrep

Free lesson

APhA NACDS MTM Elements

The first lesson of BCMTMS Prep Course (BCMTMS), free to read.

APhA NACDS MTM Elements

Topic: 1.1.1

Course: BCMTMS Prep Course (BCMTMS)

Audience: Pharmacists preparing for the Board Certified Medication Therapy Management Specialist (BCMTMS) certification exam

What you'll learn

  • Patient Assessment and Information Gathering -> MTM service components: identify the core APhA/NACDS MTM service elements and what information each element captures.
  • Medication-Related Problem Identification and Prioritization -> foundational workflow: distinguish where medication-related problems are found, documented, and translated into action.
  • Care Planning and Intervention Design -> patient-centered outputs: connect the personal medication record and medication action plan to practical MTM follow-through.
  • Implementation, Documentation, and Communication -> service execution: choose the best pharmacist action for intervention/referral and documentation/follow-up.
  • Follow-Up, Monitoring, Quality, and Practice Management -> continuity: decide when an MTM encounter is incomplete because monitoring, communication, or follow-up is missing.

Blueprint mapping

  • Patient Assessment and Information Gathering → MTM service components and required information capture
  • Medication-Related Problem Identification and Prioritization → identify issues within the MTM framework
  • Care Planning and Intervention Design → translate findings into patient-facing and clinician-facing outputs
  • Implementation, Documentation, and Communication → document services and communicate recommendations
  • Follow-Up, Monitoring, Quality, and Practice Management → determine appropriate follow-up after MTM services

Estimated time: 45-60 minutes

Prereqs: None in this course yet; forward links: CMR Versus TMR, PMR And MAP Design

Key outputs: You should be able to identify all five MTM core elements, decide what belongs in each one, spot incomplete MTM documentation, and choose the safest pharmacist action when intervention, referral, or follow-up is needed.

Why it matters

  • BCMTMS questions often test service structure before clinical detail; if you cannot identify the MTM element, you may choose the wrong next step even when the drug issue itself is obvious.
  • MTM is not just “finding a problem.” It requires converting findings into patient-friendly outputs, pharmacist documentation, communication, and follow-up.
  • Many distractors mix up what the patient receives versus what the pharmacist documents internally; knowing this split prevents easy point losses.
  • These elements create the framework used repeatedly in later topics such as CMR versus TMR and PMR/MAP design.

Key Terms & Must-Know Facts

Key terms

  • MTM: pharmacist-provided, patient-centered services to optimize therapeutic outcomes.
  • APhA/NACDS Core Elements: the commonly taught five-part MTM service structure.
  • Medication Therapy Review (MTR): structured review of medications to identify medication-related problems.
  • Comprehensive Medication Review (CMR): complete, interactive review of the full regimen and medication experience.
  • Targeted Medication Review (TMR): focused review of specific problems or gaps.
  • Personal Medication Record (PMR): patient-facing medication list.
  • Medication-Related Action Plan (MAP): patient-facing list of actions the patient should take.
  • Intervention/Referral: communication to prescriber, caregiver, or other clinician when action beyond patient education is needed.
  • Documentation: defensible record of assessment, findings, actions, and follow-up plan.
  • Follow-up: planned reassessment after the MTM service.
  • Medication-related problem: issue involving indication, effectiveness, safety, adherence, duplication, omission, or monitoring gap.
  • Transitions of care: medication management during movement between settings.

Must-know facts

  • The five core elements are MTR, PMR, MAP, intervention/referral, and documentation/follow-up.
  • The PMR and MAP are patient-facing; documentation is primarily clinician/service-facing.
  • An MTM encounter can identify a problem correctly yet still be incomplete if communication or follow-up is missing.
  • The MAP is action-oriented; it tells the patient what to do, not the clinician what was assessed.
  • The PMR should reflect what the patient is actually using, not just what is on file.
  • Intervention/referral is required when the issue exceeds routine counseling or needs another clinician’s action.
  • Documentation should support continuity, billing/workflow where applicable, and medicolegal defensibility.
  • For BCMTMS, the pharmacist should choose clarify, recommend, communicate, monitor, refer, or escalate rather than act outside scope.
Fig 1. Five core MTM elements map
Exam takeaway: Use the five-element sequence to decide what output belongs to the patient, the prescriber, or the pharmacist record.
flowchart LR
A[Medication Therapy Review] --> B[Personal Medication Record]
A --> C[Medication-Related Action Plan]
A --> D[Intervention or Referral]
D --> E[Documentation and Follow-up]
B --> E
C --> E

See Fig 1 for the high-yield relationship among the five elements.

Element Primary audience Main purpose Common exam cue
MTR Pharmacist and patient interaction Identify medication-related problems “Review the regimen and identify highest-priority problem”
PMR Patient/caregiver Current medication list for ongoing reference “Provide an updated take-home medication list”
MAP Patient/caregiver Convert findings into patient action steps “What should the patient do next?”
Intervention/Referral Prescriber/care team/other clinician Communicate recommended changes or need for evaluation “Notify prescriber” or “refer urgently”
Documentation/Follow-up Pharmacist/service record Record what happened and plan reassessment “Best documentation element” or “appropriate follow-up plan”

Core content

1.1.1.1 Foundational structure: what the five MTM elements are and how they fit together

A. Explanation

The first exam decision conflict is simple but heavily tested: is the stem asking about the review process, the patient handout, the clinician communication, or the service record? The single rule that resolves it is this: MTR is the assessment; PMR and MAP are patient-facing outputs; intervention/referral is the clinician-facing action; documentation/follow-up closes the loop. If you keep those buckets separate, most introductory MTM questions become straightforward.

WHY THIS IS TESTED: test writers often present one correct clinical idea but ask for the wrong deliverable. For example, a recommendation to obtain renal labs is not itself a MAP item unless written as a patient action; likewise, a medication list is not documentation just because the pharmacist created it.

In practical MTM workflow, the pharmacist begins with a medication therapy review, which may be comprehensive or focused. From that review come patient-facing tools: an accurate PMR and a prioritized MAP. If the pharmacist identifies a problem requiring action by another clinician, intervention or referral follows. The encounter is not complete until documentation captures the problem, recommendation, communication, and follow-up plan. See Fig 1.

Concept flow: Element recognition sequence
Start with the task
Ask whether the stem is about assessing, giving the patient a tool, contacting another clinician, or recording the service.

Sort by audience
Patient-facing means PMR or MAP. Clinician-facing means intervention/referral. Internal service record means documentation/follow-up.

Tie back to MTR
All later elements should be traceable to findings from the medication review.

Memory anchor: Think “Review, Record, Respond, Relay, Reassess” = MTR, PMR, MAP, intervention/referral, documentation/follow-up. The two patient outputs sit in the middle.
Pharmacist Action: NOTICE: whether the question asks for assessment, patient output, communication, or recordkeeping. SAY: “I reviewed your medicines, updated your list, and identified next steps we need to communicate.” MONITOR: completion of patient handouts and clinician communication during the same encounter. HOLD/CLARIFY/ESCALATE: clarify if a recommendation requires prescriber authorization or urgent evaluation.

B. Worked example

A 71-year-old woman with type 2 diabetes, hypertension, and osteoarthritis brings metformin 1000 mg by mouth twice daily, lisinopril 20 mg daily, hydrochlorothiazide 25 mg daily, ibuprofen 400 mg three times daily as needed, and an outdated bottle of glyburide she says she “sometimes still takes.” She reports dizziness and missed meals, but her distracting laboratory value is a stable LDL of 82 mg/dL. During the pharmacist visit, the learner is asked which APhA/NACDS MTM element is best represented by “give the patient a current list of what she should and should not be taking.”

Reasoning chain: identify task → this is not asking for problem identification itself, but for a patient take-home tool. Extract key facts → multiple actual and outdated medications, so the patient needs an accurate medication list. Apply rule → the patient-facing current medication list is the PMR. Eliminate distractors → MAP would list actions such as “stop using old glyburide until clarified” or “call clinic about dizziness”; intervention/referral would be contact with the prescriber; documentation would be the pharmacist record. Verify → the request centers on a current list for patient reference, so PMR is best.

C. Exam trap

Common wrong answer: Medication-related action plan.
WHY IT IS TEMPTING: The patient clearly needs to do something, and students often equate every patient handout with the MAP.
The SINGLE CLUE that eliminates it: The stem asks for a current list of medications, which is a PMR, not a task list.

D. Checkpoint

Question: During an MTM visit, a pharmacist identifies duplicate NSAID use and gives the patient an updated list of all prescription and nonprescription products currently being taken. Which MTM element is most directly represented by that take-home list?

  1. A. Medication therapy review — Tempting because the list comes from the review, but the review is the assessment process, not the take-home document.
  2. B. Personal medication record — Correct because it is the patient-facing, updated medication list intended for ongoing reference.
  3. C. Medication-related action plan — Tempting because patient action is important, but this option would list tasks, not the regimen itself.
  4. D. Intervention/referral — Tempting because duplicate NSAID use may require prescriber contact, but the question asks about the list given to the patient.
If you missed this: Review 1.1.1.1 Foundational structure: what the five MTM elements are and how they fit together — focus on the audience rule: patient-facing list = PMR.

1.1.1.2 MTR as the assessment engine: what the pharmacist is deciding during review

A. Explanation

The second decision conflict is choosing between performing a review and acting on the review. The medication therapy review is the core analytic step. It is where the pharmacist collects, reconciles, and evaluates all available medication information to identify medication-related problems involving indication, effectiveness, safety, and adherence. The single finding that resolves many questions is whether the pharmacist is still analyzing the regimen or has already moved to output/action.

WHY THIS IS TESTED: MTM stems often include a clinically interesting issue—duplicate therapy, omitted statin, affordability barrier, or monitoring gap—but the actual question asks which MTM element is being performed. If the pharmacist is still identifying and prioritizing problems, that is MTR.

MTR is broad enough to include medication history verification, assessment of OTC and herbals, review of adherence and affordability, screening for high-risk use, and identification of preventive care gaps tied to medication management. It does not end with merely spotting a discrepancy; the pharmacist must prioritize issues based on urgency, safety, and feasibility. In later lessons, you will separate CMR versus TMR; for now, the key is that both are forms of review under the MTR umbrella. See Fig 2 for how assessment categories feed problem detection.

Concept flow: MTR decision path
Collect and verify
Use patient interview plus external sources to confirm actual medication use.

Assess the four domains
Check indication, effectiveness, safety, and adherence for each relevant therapy.

Prioritize
Address urgent harm first, then high-impact chronic issues, then optimization and education.

Translate findings
Move prioritized problems into PMR, MAP, intervention/referral, and documentation.

Fig 2. MTR assessment domains
Exam takeaway: When the pharmacist is identifying indication, effectiveness, safety, or adherence problems, the service element is the medication therapy review.
flowchart TD
A[Medication list and patient interview] --> B{Assess domain}
B --> C[Indication]
B --> D[Effectiveness]
B --> E[Safety]
B --> F[Adherence]
C --> G[Need for therapy? Duplication?]
D --> H[Working? Right intensity?]
E --> I[Interactions? Contraindication? Monitoring?]
F --> J[Cost? Understanding? Access?]
G --> K[Prioritized problem list]
H --> K
I --> K
J --> K

See Fig 2 for the four-domain lens used inside the MTR.

Recall: This is the first topic in the course, so build the default habit now: every MTM question can be organized as review findings, patient outputs, clinician communication, and follow-up. Upcoming topics on CMR versus TMR will refine the review type without changing this core framework.
High-Yield Connection: This concept is tested alongside medication reconciliation and indication/effectiveness/safety/adherence classification. Know both the MTM element and the problem category for exam day — they are frequently paired in stems.
Pharmacist Action: NOTICE: duplicate therapy, missing therapy, unsafe combinations, or adherence barriers during the review. SAY: “I want to confirm what you actually take, including OTCs and old bottles, so I can identify the most important issues.” MONITOR: completeness of the regimen and whether urgent risks are addressed before lower-priority optimization. HOLD/CLARIFY/ESCALATE: escalate immediately if the review identifies red-flag toxicity, severe adverse effects, or urgent symptoms.

B. Worked example

A 63-year-old man with heart failure, atrial fibrillation, and chronic kidney disease presents for an MTM visit after multiple refill gaps. His medications include apixaban 5 mg by mouth twice daily, furosemide 40 mg daily, metoprolol succinate 100 mg daily, and naproxen 220 mg twice daily purchased over the counter. He also reports taking “a water pill from years ago” but cannot identify it. A distracting clue is that he says his multivitamin is “heart healthy.” The pharmacist’s immediate task is to determine which MTM element best describes reviewing all current prescription, OTC, and leftover medications to identify duplicate diuretic use and NSAID-related safety risk.

Reasoning chain: identify task → the pharmacist is evaluating the regimen for problems. Extract key facts → unknown additional diuretic, OTC naproxen, CKD, heart failure, anticoagulant use. Apply rule → this is the medication therapy review. Eliminate distractors → PMR would be the final corrected list; MAP would tell the patient to stop self-adjusting or contact providers; intervention/referral would communicate findings to prescribers; documentation/follow-up would record the encounter. Verify → because the pharmacist is still in the analytic phase, MTR is best.

C. Exam trap

Common wrong answer: Intervention/referral.
WHY IT IS TEMPTING: The scenario contains a real safety issue, so learners jump immediately to prescriber communication.
The SINGLE CLUE that eliminates it: The stem asks about reviewing medications to identify the problems, which occurs during MTR before communication is executed.

D. Checkpoint

Question: A pharmacist interviews a patient, reconciles pharmacy claims with pill bottles, and identifies nonadherence to rosuvastatin plus duplication between OTC ibuprofen and prescription meloxicam. Which MTM element is being performed at that moment?

  1. A. Medication therapy review — Correct because the pharmacist is actively gathering and assessing information to identify medication-related problems.
  2. B. Personal medication record — Tempting because the reconciled information may later populate the PMR, but the step described is assessment, not the handout.
  3. C. Medication-related action plan — Tempting because action steps will follow, but the stem has not yet shifted into a patient task list.
  4. D. Documentation/follow-up — Tempting because good MTM requires recording the findings, but the current activity is still the review itself.
If you missed this: Review 1.1.1.2 MTR as the assessment engine: what the pharmacist is deciding during review — focus on the discriminator “identifying problems” = MTR.
Quick Recall:

  • The MTM element that identifies medication-related problems is MTR.
  • True or False: A PMR is primarily an internal documentation tool. False.
  • Name the 4 core assessment domains used in review: indication, effectiveness, safety, adherence.

1.1.1.3 Patient-facing outputs: PMR and MAP are not interchangeable

A. Explanation

The most common foundational confusion is mixing the personal medication record with the medication-related action plan. Both are patient-facing, but they solve different problems. The PMR answers: “What medicines am I using?” The MAP answers: “What should I do next?” That single rule resolves nearly every PMR-versus-MAP question.

WHY THIS IS TESTED: Exam stems often include a medication list and a task list in the same vignette. Distractors exploit learners who recognize that the patient needs both but cannot identify which document a given statement belongs in. The PMR should be accurate, current, and understandable to the patient. The MAP should be prioritized, actionable, and written in plain language.

Examples of PMR content include drug name, strength, directions, purpose if helpful, and special notes such as allergies or what the patient actually takes. Examples of MAP content include “Schedule your blood pressure check this week,” “Ask your doctor whether you should continue glyburide,” or “Use a pillbox and bring all medicines to the next visit.” MAP items should be framed as patient actions, not internal clinical commentary. See Fig 3.

Concept flow: PMR versus MAP split
Ask what the statement does
Does it describe a medication currently used, or a task the patient should complete?

Choose the document
Medication details go to PMR. Patient action steps go to MAP.

Keep it patient-friendly
Use plain language, clear priorities, and avoid internal chart-note wording.

Fig 3. PMR versus MAP comparison flow
Exam takeaway: If the content is “what you take,” choose PMR; if it is “what you should do,” choose MAP.
flowchart LR
A[Patient-facing item] --> B{Type of content}
B -->|Current medicine list| C[PMR]
B -->|Patient task or follow-up step| D[MAP]
C --> E[Drug name, dose, directions, notes]
D --> F[Call, schedule, bring, monitor, ask, avoid]

See Fig 3 for the fastest test-day rule to separate PMR from MAP.

Patient handout layout with PMR and MAP sections
Exam takeaway: Visually separating the medication list from action steps reduces PMR-versus-MAP confusion on exam stems.

Patient handout layout with PMR and MAP sections
Memory anchor: (PMR = My Meds); (MAP = My Moves). If it helps the patient remember the regimen, think PMR. If it tells the patient what action to take, think MAP.
Pharmacist Action: NOTICE: whether the patient needs a corrected regimen list, a prioritized task list, or both. SAY: “This page lists every medicine you take; this second page lists the next steps for you.” MONITOR: patient understanding using teach-back during the encounter and update after changes. HOLD/CLARIFY/ESCALATE: clarify immediately if the patient is using old, duplicate, or stopped medications that make the PMR inaccurate.

B. Worked example

A 68-year-old man with COPD, coronary artery disease, and insomnia uses tiotropium daily, albuterol inhaler as needed, aspirin 81 mg daily, and diphenhydramine 50 mg nightly purchased over the counter. He reports “sometimes borrowing” his spouse’s omeprazole. The distracting clue is that his blood pressure today is controlled. The pharmacist completes an MTM visit and wants to provide two patient documents: one showing the actual current regimen, and one listing steps such as “stop using your spouse’s medicine,” “bring inhalers to the next visit,” and “ask your clinician about nighttime sleep options.”

Reasoning chain: identify task → two patient-facing outputs are needed. Extract key facts → one need is for an accurate regimen list; the other is for specific follow-up tasks. Apply rule → current regimen = PMR; next steps = MAP. Eliminate distractors → intervention/referral may still occur for anticholinergic burden or unsafe borrowing, but those are separate clinician communications. Verify → if the exam asks which element contains the stepwise patient tasks, the answer is MAP.

C. Exam trap

Common wrong answer: PMR for statements like “call your doctor about dizziness.”
WHY IT IS TEMPTING: Students see a patient-facing document and stop there.
The SINGLE CLUE that eliminates it: The statement is an action the patient should take, so it belongs in the MAP.

D. Checkpoint

Question: Which statement best belongs in a patient’s medication-related action plan rather than the personal medication record?

  1. A. Metoprolol succinate 50 mg by mouth once daily for blood pressure — Tempting because it is patient-friendly, but it describes a medication entry and belongs in the PMR.
  2. B. Allergic reaction to sulfonamides: rash — Tempting because it is clinically important and may be listed with the PMR, but it is not a patient action step.
  3. C. Bring all prescription and over-the-counter medicines to your next visit — Correct because it is a plain-language action the patient should complete.
  4. D. Vitamin D 1000 units once daily — Tempting because supplements are often forgotten, but this is still a medication list item for the PMR.
If you missed this: Review 1.1.1.3 Patient-facing outputs: PMR and MAP are not interchangeable — focus on the discriminator “what you take” versus “what you do.”

1.1.1.4 Intervention, referral, documentation, and follow-up: closing the MTM loop

A. Explanation

The final foundational decision conflict is choosing between educating the patient and taking the next professional action required to resolve the problem. Not every medication-related problem can be solved within the patient conversation alone. If the issue requires a prescriber’s order, diagnostic workup, urgent evaluation, or care-team coordination, the pharmacist must perform intervention/referral. After that, the pharmacist must document the encounter and establish follow-up.

WHY THIS IS TESTED: many stems reward candidates who can recognize when the pharmacist’s role is to recommend, clarify, refer, or escalate rather than independently change therapy. Just as important, many stems test whether follow-up is specific enough to ensure continuity.

Intervention/referral includes communicating suggestions such as dose reassessment, need for lab monitoring, duplicate therapy resolution, refill-gap discussion, or urgent symptom evaluation. Documentation should capture the identified problem, the rationale, who was contacted, what was recommended, patient education provided, and planned follow-up. Follow-up must match risk: a life-threatening issue requires immediate escalation; a routine adherence aid can be reassessed later. See Fig 4 for the decision path. This section is where MTM most clearly intersects with professional scope: the pharmacist acts decisively, but within authority.

Concept flow: From finding to closure
Identify the problem
Confirm whether the issue can be handled by counseling alone or needs external action.

Choose route
If prescriber or urgent evaluation is needed, intervene or refer. If patient task is enough, reinforce through MAP.

Document
Record the issue, recommendation, communication, and patient counseling provided.

Plan follow-up
Set timing based on urgency, monitoring need, and whether the recommendation was implemented.

Fig 4. Escalate versus document decision tree
Exam takeaway: When a finding requires another clinician’s action or urgent evaluation, choose intervention/referral first, then document and arrange follow-up.
flowchart TD
A[Problem identified during MTR] --> B{Can patient self-act safely?}
B -->|Yes| C[Add to MAP and counsel]
B -->|No| D[Intervention or referral]
D --> E{Urgent risk?}
E -->|Yes| F[Immediate escalation]
E -->|No| G[Routine prescriber communication]
C --> H[Document]
F --> H
G --> H
H --> I[Follow-up plan]

See Fig 4 for the choose-versus-escalate logic.

Pharmacist documenting and messaging prescriber
Exam takeaway: MTM is incomplete without a defensible note and clear communication plan when another clinician must act.
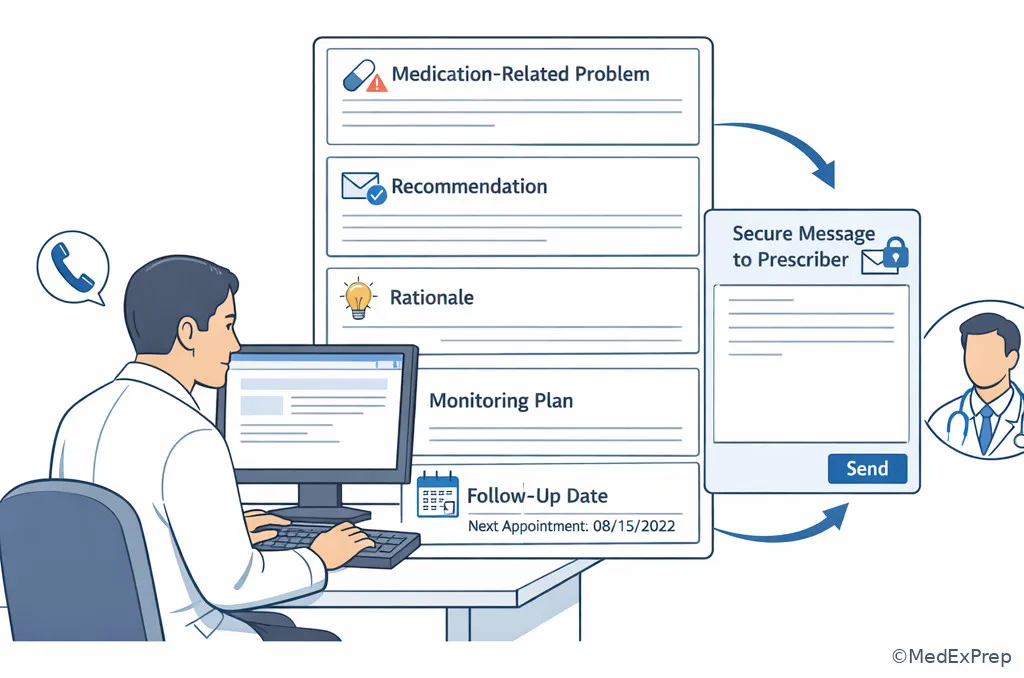
Pharmacist documenting and messaging prescriber
Key rule: If the patient has a red-flag medication safety issue or symptoms needing urgent assessment, the pharmacist should escalate immediately; do not treat documentation as the next step when safety action comes first.
High-Yield Connection: This concept is tested alongside transitions-of-care reconciliation and SBAR/SOAP communication. Know both the problem and the handoff structure — exam stems often ask what to communicate, not just what to think.
Pharmacist Action: NOTICE: whether the issue requires counseling only, prescriber action, or urgent referral. SAY: “I’m concerned this needs review by your clinician today, and I will document and communicate the recommendation.” MONITOR: completion of communication, response status, and patient follow-up interval based on risk. HOLD/CLARIFY/ESCALATE: escalate immediately for severe adverse effects, suspected toxicity, dangerous interactions, or red-flag symptoms.

B. Worked example

A 76-year-old woman with atrial fibrillation, heart failure, and recent hospital discharge is seen in community MTM. Her list includes warfarin 5 mg nightly, amiodarone 200 mg daily, furosemide 20 mg daily, and trimethoprim-sulfamethoxazole started yesterday at urgent care. She reports gum bleeding and dark stools but says she mainly came in to ask about a calcium supplement. The distracting clue is that she also forgot one warfarin dose last week. The pharmacist must choose the most appropriate MTM action.

Reasoning chain: identify task → urgent safety triage within pharmacist scope. Extract key facts → warfarin plus TMP-SMX interaction, bleeding symptoms, recent discharge, amiodarone interaction. Apply rule → this exceeds simple counseling; urgent evaluation/referral is needed, then documentation and communication. Eliminate distractors → updating the PMR is necessary but not sufficient; adding a MAP item alone delays urgent care; merely documenting without escalation is unsafe. Verify → the highest-priority MTM element now is intervention/referral with immediate escalation, followed by documentation/follow-up.

C. Exam trap

Common wrong answer: Add the interaction concern to the MAP and recheck next week.
WHY IT IS TEMPTING: MAP feels patient-centered and follow-up-oriented.
The SINGLE CLUE that eliminates it: Dark stools and bleeding signal urgent safety risk, so immediate referral/escalation is required.

D. Checkpoint

Question: During an MTM encounter, a pharmacist finds that a patient recently started clarithromycin while taking simvastatin 40 mg nightly and is now reporting new severe muscle pain and weakness. What is the most appropriate MTM element to prioritize first?

  1. A. Personal medication record — Tempting because the list needs updating, but it does not address the immediate safety concern.
  2. B. Medication-related action plan — Tempting because the patient needs instructions, but clinician-level and urgent action come first.
  3. C. Intervention/referral — Correct because a serious interaction with concerning symptoms requires prompt communication and urgent evaluation.
  4. D. Documentation/follow-up — Tempting because every encounter must be documented, but documentation follows the urgent safety action.
If you missed this: Review 1.1.1.4 Intervention, referral, documentation, and follow-up: closing the MTM loop — focus on the discriminator “urgent risk requires intervention/referral before documentation.”
Quick Recall:

  • The most urgent MTM action when a dangerous interaction causes alarming symptoms is intervention/referral.
  • True or False: Documentation can replace communication if the pharmacist note is detailed enough. False.
  • Name the 3 core closure items after a clinician-facing recommendation: document, communicate, follow up.

1.1.1.5 Integration: using the MTM elements to choose the best next step in board-style cases

A. Explanation

Once you know the five elements, the board-style challenge becomes integration: which element is the best answer for this exact moment in the case? The resolving rule is to identify the task the pharmacist must complete next, not every reasonable activity that could eventually happen. In most questions, multiple MTM elements are appropriate over the full encounter. The exam asks for the highest-priority next step.

WHY THIS IS TESTED: realistic MTM practice is sequential. A patient may need an MTR, PMR, MAP, prescriber communication, and follow-up—all in one episode. The test discriminates whether you can choose the first necessary action based on urgency, audience, and scope.

A reliable strategy is: identify urgency first; then identify audience; then identify output. If there is immediate danger, choose intervention/referral. If the pharmacist is still detecting problems, choose MTR. If the patient needs a current list, choose PMR. If the patient needs task-oriented instructions, choose MAP. If the question is about defensible recordkeeping or continuity, choose documentation/follow-up. See Fig 5.

Concept flow: Best-next-step selector
Check urgency
Red flags or dangerous interactions push you to intervention/referral.

Check phase
Still gathering and analyzing means MTR.

Check audience
Patient list = PMR; patient tasks = MAP; clinician communication = intervention/referral.

Close the loop
Documentation and follow-up complete the service.

Fig 5. Best-next-step MTM selector
Exam takeaway: In integrated cases, choose the MTM element that matches the immediate task, not every action that will eventually occur.
flowchart TD
A[Board-style MTM case] --> B{Urgent safety issue?}
B -->|Yes| C[Intervention or referral]
B -->|No| D{Still identifying problems?}
D -->|Yes| E[MTR]
D -->|No| F{Need patient output?}
F -->|Medication list| G[PMR]
F -->|Action steps| H[MAP]
C --> I[Document and follow-up]
E --> I
G --> I
H --> I

See Fig 5 for a compact test-day algorithm.

MTM case triage board with next-step choices
Exam takeaway: Sorting the case by urgency, audience, and output quickly narrows the correct MTM element.
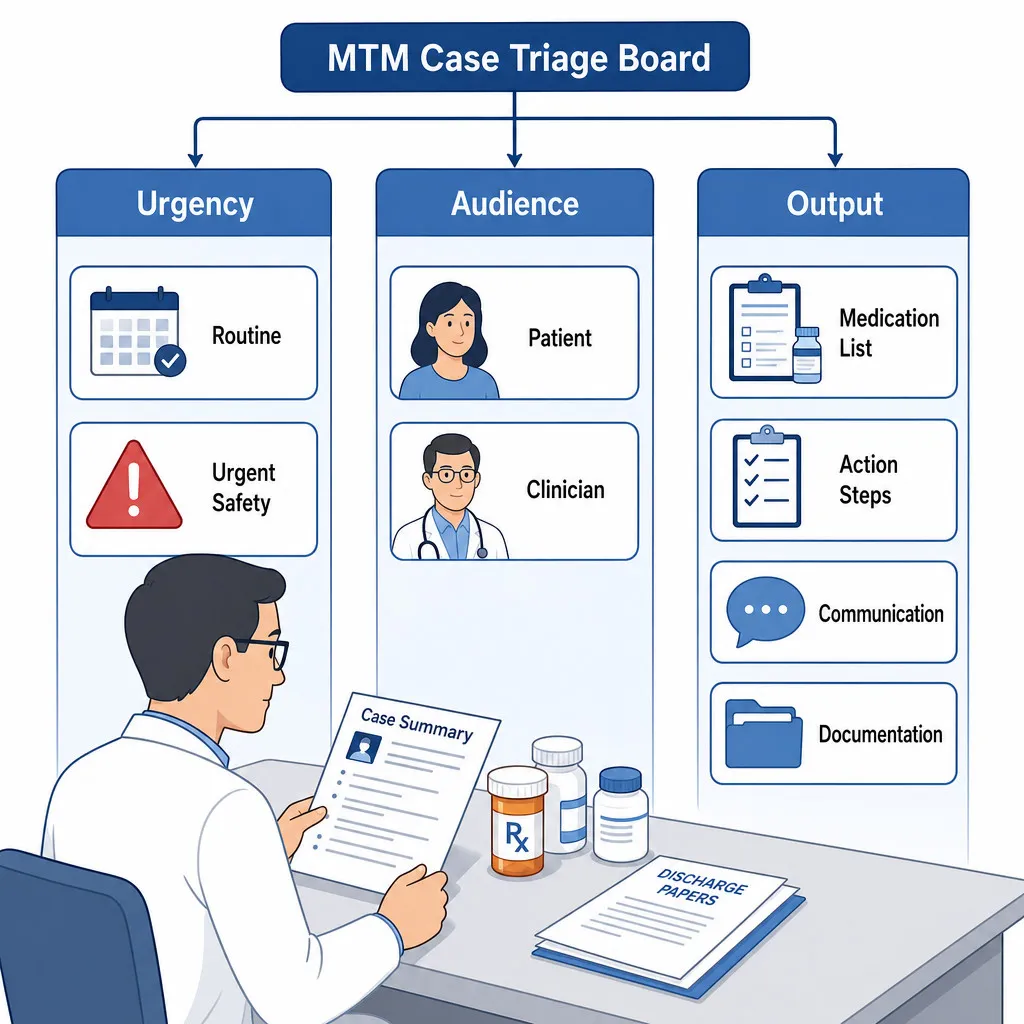
MTM case triage board with next-step choices
Recall: In upcoming CMR Versus TMR, you will refine the type of review. Here, build the larger frame first: regardless of review depth, the pharmacist still converts findings into PMR, MAP, intervention/referral, and documentation/follow-up.
Pharmacist Action: NOTICE: what the question is truly asking for right now, not what could happen later. SAY: “My first priority is to address the safety issue; after that I will update your medication list and next steps.” MONITOR: whether the chosen action solves the immediate problem and whether downstream MTM elements are completed. HOLD/CLARIFY/ESCALATE: if authority or protocol is unclear, verify local process and communicate recommendations rather than assuming autonomous prescriptive power.

B. Worked example

A 59-year-old woman with diabetes, depression, and recent hospitalization for pneumonia comes for an MTM visit with metformin 1000 mg twice daily, insulin glargine 20 units nightly, sertraline 100 mg daily, and prednisone 40 mg daily started 2 days ago. She forgot her hospital discharge papers and says she might still be taking her old glipizide. Her distracting clue is that she asks whether she should take vitamins with breakfast. The pharmacist identifies possible duplicate diabetes therapy, steroid-related hyperglycemia risk, and uncertainty about what was stopped at discharge.

Reasoning chain: identify task → if asked for the first structured MTM step, the pharmacist must clarify the active regimen and identify problems. Extract key facts → possible duplicate therapy and incomplete discharge information. Apply rule → the best next MTM element is MTR. Eliminate distractors → PMR cannot be accurate until the regimen is verified; MAP would be premature before clarification; intervention/referral may come later if unsafe overlap is confirmed; documentation follows the review. Verify → best answer is the review process first.

C. Exam trap

Common wrong answer: PMR immediately after hearing the patient’s story.
WHY IT IS TEMPTING: The patient clearly needs a clean medication list after hospitalization.
The SINGLE CLUE that eliminates it: The current regimen is still uncertain; the pharmacist must perform MTR and reconciliation before the PMR can be accurate.

D. Checkpoint

Question: A patient asks, “What exactly should I do before my next doctor’s visit?” The pharmacist has already completed medication review, updated the regimen list, and sent a recommendation to the prescriber. Which MTM element best addresses the patient’s question?

  1. A. Medication therapy review — Tempting because it generated the findings, but the review phase is already complete.
  2. B. Personal medication record — Tempting because the regimen list helps the patient, but the question asks for action steps rather than medication details.
  3. C. Medication-related action plan — Correct because it converts findings into specific patient tasks to complete before follow-up.
  4. D. Documentation/follow-up — Tempting because the encounter needs closure, but this answer does not directly give the patient next actions.
If you missed this: Review 1.1.1.5 Integration: using the MTM elements to choose the best next step in board-style cases — focus on choosing the element that matches the immediate task and audience.

Exam Traps & Differentiators

Most common wrong answer and why: MAP instead of PMR. This is tempting because both are patient-facing and often delivered together. The discriminator is whether the content describes the current medication regimen or tells the patient what to do next.

Looks similar Why learners confuse it Single clue that separates it Correct MTM element
Updated medication list vs task list Both are patient handouts Medication details = list; action verbs = tasks PMR vs MAP
Finding a discrepancy vs calling the prescriber Both occur in the same encounter Identifying the issue = review; communicating change = intervention MTR vs intervention/referral
Note in chart vs message to clinician Both are professional communications Internal record = documentation; external action request = intervention Documentation vs intervention/referral
Patient education vs urgent triage Both involve advising the patient Red-flag symptoms or toxic interaction require escalation Intervention/referral
Creating PMR before reconciliation Patient needs a list quickly Uncertain regimen means review first MTR first

If the stem says ... think ...

  • “Provide the patient with a current list” → think PMR.
  • “Tell the patient what to do before the next visit” → think MAP.
  • “Review all medications to identify problems” → think MTR.
  • “Communicate recommendation to prescriber” → think intervention/referral.
  • “Record the encounter and plan reassessment” → think documentation/follow-up.
  • “New dangerous symptoms or severe interaction” → think urgent referral/escalation before routine documentation.
Comparison chart of MTM deliverables in practice
Exam takeaway: Side-by-side visual cues help separate patient handouts, clinician communication, and internal documentation.
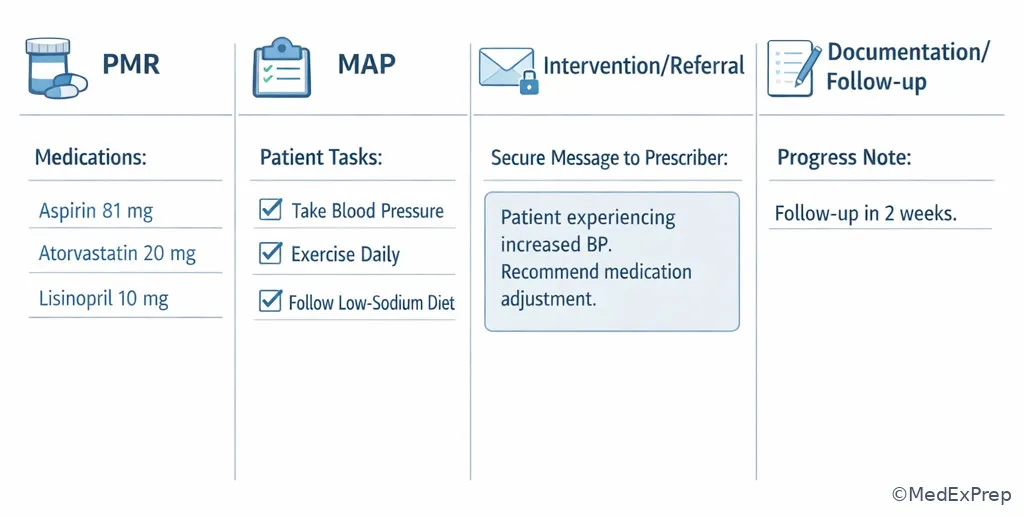
Comparison chart of MTM deliverables in practice

Related confusable pairs from upcoming topics include CMR versus TMR and PMR versus MAP design. Those later lessons go deeper into review scope and document construction, but the trap here is more basic: know which element the stem is asking about before worrying about format details.

Review connection: The traps above test element identification and next-step selection. If any felt unfamiliar, revisit 1.1.1.3 Patient-facing outputs: PMR and MAP are not interchangeable and 1.1.1.4 Intervention, referral, documentation, and follow-up: closing the MTM loop before attempting the Self-check quiz.

Tables

Key fact/value table High-yield point
Number of core APhA/NACDS MTM elements 5
Patient-facing elements PMR and MAP
Assessment element MTR
Clinician-facing action element Intervention/referral
Closure element Documentation/follow-up
Priority rule Urgent safety issues outrank routine education and paperwork
Best PMR cue Current medication list the patient can use
Best MAP cue Plain-language patient action steps
Comparison item PMR MAP Documentation/follow-up
Primary user Patient/caregiver Patient/caregiver Pharmacist/care team record
Main question answered What do I take? What should I do? What happened and what is next?
Typical content Name, dose, directions, notes Call, schedule, bring, avoid, monitor Problem, recommendation, communication, follow-up
Exam distractor Chosen for any patient handout Chosen for any patient-friendly sentence Chosen when clinician communication is actually needed
Best discriminator Regimen list Action verb Record + reassessment plan
Case cue Likely classification Why
Pharmacist compares bottles, claims, and interview to identify duplicate therapy MTR Assessment and problem detection are occurring
Patient receives a corrected home medication list after discharge clarification PMR Current regimen is being presented to the patient
Patient receives instructions to bring inhalers and schedule A1c testing MAP Action steps are directed to the patient
Pharmacist contacts prescriber about ACE inhibitor omission Intervention/referral Another clinician must act on the recommendation
Pharmacist records problem list, recommendation, and 2-week reassessment Documentation/follow-up The service is being closed and tracked
Patient on warfarin reports melena after interacting antibiotic started Urgent intervention/referral first Safety escalation outranks routine handouts and note completion

Algorithm / Approach

Concept flow: MTM element selection algorithm
Start
Read the stem and define the pharmacist task in one phrase: review, give patient tool, communicate, or document.

Safety decision
If urgent symptoms, toxicity, or dangerous interaction are present → intervention/referral immediately. Otherwise continue.

Assessment versus output
If still identifying problems → MTR. If the regimen is already clarified and the patient needs a list → PMR.

Patient task versus clinician task
Patient action steps → MAP. Prescriber/care team communication → intervention/referral.

Close
Document the encounter and set follow-up timing based on risk, implementation, and monitoring needs.

Fig 6. MTM workflow desk reference
Exam takeaway: A simple urgency-audience-output checklist prevents choosing a technically correct but mistimed MTM element.
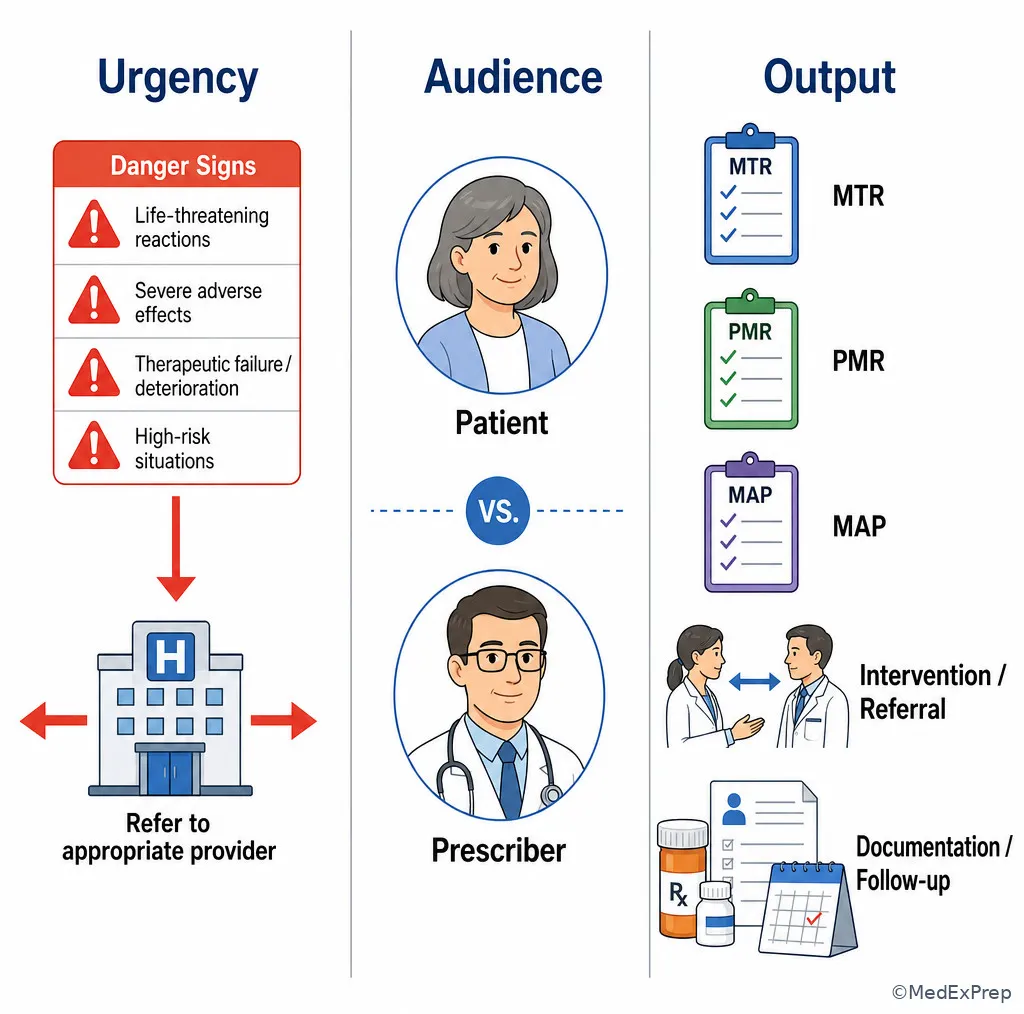
Fig 6. MTM workflow desk reference

See Fig 6 as a compact exam-day mental checklist.

Rapid Review

  • MTR → identifies problems; not the same as the final recommendation.
  • PMR → current medication list; think “what I take.”
  • MAP → patient task list; think action verbs.
  • Intervention/referral → another clinician must act or patient needs urgent evaluation.
  • Documentation/follow-up → closes the loop and supports continuity.
  • Urgent symptom + interaction → escalate before routine paperwork.
  • Unclear discharge regimen → reconcile and review before generating PMR.
  • Patient handout with drug names and directions → PMR, not MAP.
  • Patient handout with “call,” “bring,” or “schedule” → MAP, not PMR.
  • Prescriber message recommending change → intervention/referral, not documentation alone.
  • Found the issue but did not communicate it → MTM process incomplete.
  • Good note but no follow-up for unresolved issue → closure gap.
Memory anchor: (List = PMR); (To-do = MAP); Tell clinician = intervention; Tell chart = documentation. If you can say the sentence aloud, you can usually pick the right element fast.

Self-check quiz

1. A pharmacist completes an MTM visit for a 67-year-old man with hypertension and hyperlipidemia taking amlodipine 10 mg by mouth daily and atorvastatin 40 mg by mouth nightly. The patient asks for a take-home list of all medications, doses, and directions. Which is the most appropriate MTM element?

  1. A. Medication therapy review
  2. B. Personal medication record
  3. C. Medication-related action plan
  4. D. Documentation/follow-up

2. A pharmacist has already reviewed a patient’s regimen and updated the medication list. The patient taking lisinopril 20 mg by mouth daily and metformin 500 mg by mouth twice daily asks, “What should I do before my next appointment?” Which MTM element best answers that question?

  1. A. Medication therapy review
  2. B. Personal medication record
  3. C. Medication-related action plan
  4. D. Intervention/referral

3. A 74-year-old woman with CKD and osteoarthritis brings losartan 50 mg by mouth daily, meloxicam 15 mg by mouth daily, ibuprofen 400 mg by mouth three times daily as needed, and an old bottle of naproxen. Her serum creatinine from last month is mildly elevated, and the distracting detail is that she also asks about fish oil. The pharmacist compares all bottles with pharmacy fill history to identify duplicate NSAID use. Which MTM element is being performed?

  1. A. Medication therapy review
  2. B. Personal medication record
  3. C. Intervention/referral
  4. D. Documentation/follow-up

4. A 69-year-old man with diabetes and coronary disease takes metformin 1000 mg by mouth twice daily, insulin glargine 18 units subcutaneously nightly, and aspirin 81 mg daily. After the review, the pharmacist writes “Bring your glucose log, schedule your eye exam, and ask your clinician whether glipizide should remain discontinued.” Which MTM element is this?

  1. A. Personal medication record
  2. B. Medication-related action plan
  3. C. Intervention/referral
  4. D. Documentation/follow-up

5. A 72-year-old patient with atrial fibrillation and hypothyroidism takes warfarin 5 mg by mouth nightly and levothyroxine 75 mcg by mouth every morning. The patient was started on trimethoprim-sulfamethoxazole yesterday and now reports nosebleeds and dark stools; the distracting detail is that one warfarin dose was missed last week. What is the most appropriate next MTM action?

  1. A. Update the PMR first, then reassess in 1 month
  2. B. Add “watch for bleeding” to the MAP and follow up next week
  3. C. Perform intervention/referral for urgent evaluation, then document and follow up
  4. D. Complete routine documentation and wait for the prescriber to call back if concerned

6. A 61-year-old woman with heart failure, diabetes, and recent discharge takes carvedilol 12.5 mg by mouth twice daily, furosemide 40 mg by mouth daily, metformin 1000 mg by mouth twice daily, and prednisone 20 mg by mouth daily started in the hospital. She thinks she may also still be taking her old glyburide, and she did not bring discharge paperwork. The distracting detail is that she also asks whether magnesium supplements are safe. Which is the most appropriate MTM element to prioritize first?

  1. A. Personal medication record
  2. B. Medication-related action plan
  3. C. Medication therapy review
  4. D. Documentation/follow-up

7. A 78-year-old man with coronary artery disease, GERD, and chronic insomnia takes clopidogrel 75 mg by mouth daily, omeprazole 40 mg by mouth daily, and diphenhydramine 50 mg by mouth nightly. After the pharmacist identifies a potential interaction concern and inappropriate OTC use, which option best represents intervention/referral rather than MAP or documentation?

  1. A. “Bring all over-the-counter products to your next visit.”
  2. B. “I will send a recommendation to your clinician about the PPI and sedating OTC use.”
  3. C. “Current medications: clopidogrel 75 mg daily, omeprazole 40 mg daily, diphenhydramine 50 mg nightly.”
  4. D. “Problem identified, patient counseled, follow up in 2 weeks.”

8. A 70-year-old woman with hypertension, COPD, and depression uses tiotropium inhaled once daily, albuterol inhaled as needed, sertraline 100 mg by mouth daily, and leftover clonazepam 0.5 mg by mouth nightly from an old prescription. She reports increased falls and confusion, but the distracting detail is that her inhaler refill dates are on time. The pharmacist has already reviewed the regimen and updated the medication list. Which is the most appropriate next MTM element if the pharmacist wants the patient to stop using old sedatives and bring all bottles to the next appointment?

  1. A. Medication-related action plan
  2. B. Personal medication record
  3. C. Medication therapy review
  4. D. Documentation/follow-up

Answer key

1. Answer: B. Personal medication record

  • A. Medication therapy review: Tempting because the list comes from the review. Incorrect for this scenario because the stem asks for the take-home list itself, not the assessment process. Single clue: “take-home list of all medications, doses, and directions.” Source support: APhA/NACDS Core Elements and DiPiro’s MTM framework emphasize PMR as the patient medication list.
  • B. Personal medication record: Correct because the PMR is the patient-facing record of current medications, doses, and directions. The functional rationale is workflow-based rather than PK-based: it provides a reconciled regimen reference for safe use. Single clue: “list of all medications, doses, and directions.” Source support: APhA/NACDS MTM Core Elements; ASHP medication management documentation principles.
  • C. Medication-related action plan: Tempting because patient counseling usually includes next steps. Incorrect because the MAP is task-oriented, not a regimen list. Single clue: no action verbs such as call, schedule, bring, monitor. Source support: APhA/NACDS Core Elements.
  • D. Documentation/follow-up: Tempting because the pharmacist must record the service. Incorrect because documentation is the internal record and plan, not the patient’s medication list. Single clue: patient asks for a take-home list. Source support: ASHP and APhA MTM documentation standards.
If you missed this: Review 1.1.1.3 Patient-facing outputs: PMR and MAP are not interchangeable — focus on the discriminator “current medication list” = PMR.

2. Answer: C. Medication-related action plan

  • A. Medication therapy review: Tempting because review precedes recommendations. Incorrect because the stem states the review is already done. Single clue: “has already reviewed a patient’s regimen.” Source support: APhA/NACDS sequencing of MTM elements.
  • B. Personal medication record: Tempting because it is patient-facing. Incorrect because the question asks what the patient should do next, not what they take. Single clue: “What should I do before my next appointment?” Source support: APhA/NACDS Core Elements.
  • C. Medication-related action plan: Correct because the MAP translates review findings into patient action steps. Operationally, it improves execution of care plan tasks and adherence behaviors. Single clue: asks for next actions. Source support: APhA/NACDS Core Elements; Lexicomp patient-care workflow references support task-oriented counseling tools.
  • D. Intervention/referral: Tempting because some actions may involve another clinician. Incorrect because the question is specifically about what the patient should do. Single clue: patient-directed wording. Source support: APhA/NACDS MTM framework.
If you missed this: Review 1.1.1.3 Patient-facing outputs: PMR and MAP are not interchangeable — focus on the rule “what to do next” = MAP.

3. Answer: A. Medication therapy review

  • A. Medication therapy review: Correct because the pharmacist is comparing medication sources to identify duplicate NSAID use and safety risk. Clinically, NSAID duplication increases toxicity risk, but the MTM element tested is the analytic review step. Single clue: “compares all bottles with pharmacy fill history to identify.” Source support: APhA/NACDS Core Elements; DiPiro on medication assessment workflow.
  • B. Personal medication record: Tempting because a corrected list will eventually be needed. Incorrect because the pharmacist has not yet finished analyzing which agents are current and problematic. Single clue: still identifying the issue. Source support: APhA/NACDS.
  • C. Intervention/referral: Tempting because CKD plus multiple NSAIDs may require clinician communication. Incorrect because the stem centers on the review activity before communication. Single clue: no communication has yet occurred. Source support: APhA/NACDS.
  • D. Documentation/follow-up: Tempting because the findings should be recorded. Incorrect because the stem is not about recording or planning reassessment. Single clue: active medication comparison is underway. Source support: ASHP documentation guidance.
If you missed this: Review 1.1.1.2 MTR as the assessment engine: what the pharmacist is deciding during review — focus on “identifying medication-related problems” = MTR.

4. Answer: B. Medication-related action plan

  • A. Personal medication record: Tempting because it is patient-facing and may include diabetes medicines. Incorrect because the listed statements are not drug entries but tasks. Single clue: all statements use action language. Source support: APhA/NACDS Core Elements.
  • B. Medication-related action plan: Correct because the tasks are specific patient actions: bring logs, schedule exams, ask clinician about therapy status. These improve execution and continuity after the review. Single clue: “Bring,” “schedule,” and “ask.” Source support: APhA/NACDS; ASHP ambulatory care patient education frameworks.
  • C. Intervention/referral: Tempting because one task mentions asking the clinician about glipizide. Incorrect because the document is still directed to the patient rather than being a pharmacist-to-prescriber communication. Single clue: patient-oriented wording. Source support: APhA/NACDS.
  • D. Documentation/follow-up: Tempting because follow-up planning is implied. Incorrect because documentation would record the encounter internally; this is a patient task list. Single clue: intended for patient use. Source support: APhA/NACDS and ASHP documentation practices.
If you missed this: Review 1.1.1.3 Patient-facing outputs: PMR and MAP are not interchangeable — focus on the action-verb rule for MAP items.

5. Answer: C. Perform intervention/referral for urgent evaluation, then document and follow up

  • A. Update the PMR first, then reassess in 1 month: Tempting because an accurate list matters after a new antibiotic is added. Incorrect because the interaction between warfarin and trimethoprim-sulfamethoxazole can raise INR and bleeding risk quickly, and the patient already has bleeding symptoms. Single clue: “nosebleeds and dark stools.” Source support: Lexicomp interaction monograph; FDA warfarin labeling.
  • B. Add “watch for bleeding” to the MAP and follow up next week: Tempting because MAP is patient-centered and addresses bleeding. Incorrect because symptomatic possible GI bleeding requires urgent evaluation, not delayed self-monitoring. Single clue: active bleeding symptoms. Source support: Lexicomp; Clinical Pharmacology; standard anticoagulation safety guidance.
  • C. Perform intervention/referral for urgent evaluation, then document and follow up: Correct because the PD/clinical issue is a high-risk interaction plus alarming symptoms, requiring prompt escalation within pharmacist scope. Documentation and follow-up still matter but come after initiating urgent action. Single clue: warfarin + TMP-SMX with dark stools. Source support: FDA labeling, Lexicomp, and ACCP antithrombotic safety principles.
  • D. Complete routine documentation and wait for the prescriber to call back if concerned: Tempting because thorough notes are expected. Incorrect because documentation cannot substitute for urgent triage. Single clue: time-sensitive bleeding risk. Source support: ASHP patient safety principles; Lexicomp interaction severity guidance.
If you missed this: Review 1.1.1.4 Intervention, referral, documentation, and follow-up: closing the MTM loop — focus on the discriminator “red-flag symptoms override routine patient handouts or charting.”

6. Answer: C. Medication therapy review

  • A. Personal medication record: Tempting because discharge confusion makes a medication list urgently useful. Incorrect because the regimen is not yet verified; a PMR built too early may perpetuate errors. Single clue: “she may also still be taking her old glyburide” and lacks discharge paperwork. Source support: APhA/NACDS; ASHP medication reconciliation principles.
  • B. Medication-related action plan: Tempting because the patient will need instructions about diabetes monitoring and discharge follow-through. Incorrect because the pharmacist must first determine the true active regimen and safety issues. Single clue: uncertainty precedes action planning. Source support: APhA/NACDS.
  • C. Medication therapy review: Correct because the immediate need is to reconcile and assess the regimen for possible duplicate sulfonylurea use and steroid-related hyperglycemia risk. From a medication-management standpoint, this is the foundational analytic step. Single clue: unclear active medication regimen after discharge. Source support: APhA/NACDS Core Elements; DiPiro and ASHP transitions-of-care medication review guidance.
  • D. Documentation/follow-up: Tempting because a transition-of-care visit requires tracking. Incorrect because the pharmacist does not yet have enough clarified information for accurate closure. Single clue: unresolved uncertainty at the start of the encounter. Source support: ASHP documentation standards.
If you missed this: Review 1.1.1.5 Integration: using the MTM elements to choose the best next step in board-style cases — focus on the rule “uncertain regimen after transition of care = MTR first.”

7. Answer: B. “I will send a recommendation to your clinician about the PPI and sedating OTC use.”

  • A. “Bring all over-the-counter products to your next visit.” Tempting because it is good advice and supports future medication review. Incorrect because it is a patient task and therefore MAP content. Single clue: patient instruction phrased as a task. Source support: APhA/NACDS.
  • B. “I will send a recommendation to your clinician about the PPI and sedating OTC use.” Correct because this is pharmacist-to-clinician communication about optimizing therapy and reducing risk. The clinical rationale is that clopidogrel/PPI selection and anticholinergic sedative burden may require prescriber review or regimen change. Single clue: direct recommendation to clinician. Source support: Lexicomp interaction resources; APhA/NACDS intervention/referral element.
  • C. “Current medications: clopidogrel 75 mg daily, omeprazole 40 mg daily, diphenhydramine 50 mg nightly.” Tempting because it contains medication names and doses. Incorrect because it is a PMR-style entry, not clinician communication. Single clue: medication list format. Source support: APhA/NACDS PMR element.
  • D. “Problem identified, patient counseled, follow up in 2 weeks.” Tempting because it sounds professional and complete. Incorrect because it is documentation/follow-up language, not the intervention itself. Single clue: internal note style. Source support: ASHP documentation guidance; APhA/NACDS.
If you missed this: Review 1.1.1.4 Intervention, referral, documentation, and follow-up: closing the MTM loop — focus on the discriminator “message to clinician” = intervention/referral.

8. Answer: A. Medication-related action plan

  • A. Medication-related action plan: Correct because the review and PMR are already complete, and the pharmacist now wants the patient to take specific next steps: stop using old sedatives and bring all bottles. The management logic is task-oriented and patient-facing. Single clue: explicit patient actions after review completion. Source support: APhA/NACDS Core Elements.
  • B. Personal medication record: Tempting because the medication list has been updated. Incorrect because the stem asks for patient tasks, not list content. Single clue: “stop using” and “bring all bottles.” Source support: APhA/NACDS PMR versus MAP distinction.
  • C. Medication therapy review: Tempting because falls and confusion imply safety assessment. Incorrect because the stem states the pharmacist has already reviewed the regimen. Single clue: review already done. Source support: APhA/NACDS sequencing.
  • D. Documentation/follow-up: Tempting because these actions should also be recorded and reassessed. Incorrect because the question asks for the element used to tell the patient what to do next. Single clue: patient instruction focus. Source support: ASHP documentation principles; APhA/NACDS.
If you missed this: Review 1.1.1.3 Patient-facing outputs: PMR and MAP are not interchangeable — focus on the discriminator “patient tasks after review completion” = MAP.

References

  • American Pharmacists Association and National Association of Chain Drug Stores Foundation. Medication Therapy Management in Pharmacy Practice: Core Elements of an MTM Service Model. Washington, DC: APhA and NACDS Foundation.
  • American Society of Health-System Pharmacists. ASHP Guidelines on Pharmacist-Conducted Patient Education and Counseling.
  • DiPiro, Joseph T., et al. Pharmacotherapy: A Pathophysiologic Approach. McGraw-Hill.
  • Lexicomp Online. Wolters Kluwer Clinical Drug Information.
  • Clinical Pharmacology. Elsevier.
  • U.S. Food and Drug Administration. Prescribing Information for Warfarin and Other Relevant Drug Labels.

Last reviewed: March 11, 2026

Lesson 2

CMR Versus TMR

CMR Versus TMR

Topic: 1.1.2

Course: BCMTMS Prep Course (BCMTMS)

Audience: Pharmacists preparing for the Board Certified Medication Therapy Management Specialist (BCMTMS) exam

What you'll learn

  • Patient Assessment and Information Gathering -> MTM service identification: Distinguish when a case calls for a comprehensive medication review (CMR) versus a targeted medication review (TMR).
  • Medication-Related Problem Identification and Prioritization -> service scope selection: Match the intensity of review to the medication-related problem, transition event, and available information.
  • Care Planning and Intervention Design -> patient-centered MTM workflow: Select the appropriate outputs, follow-up actions, and communication elements for CMR versus TMR.
  • Implementation, Documentation, and Communication -> defensible MTM records: Document CMR and TMR encounters in a way that supports continuity, quality, and pharmacist scope.
  • Follow-Up, Monitoring, Quality, and Practice Management -> service sequencing: Decide when a TMR should trigger, precede, follow, or be converted into a CMR.

Blueprint mapping

  • Patient Assessment and Information Gathering → MTM service identification and data collection strategy
  • Medication-Related Problem Identification and Prioritization → comprehensive versus problem-focused assessment
  • Care Planning and Intervention Design → selecting service intensity and next steps
  • Implementation, Documentation, and Communication → documenting MTM encounters and communicating recommendations
  • Follow-Up, Monitoring, Quality, and Practice Management → scheduling follow-up and using TMR within longitudinal MTM workflow

Estimated time: 45-60 minutes

Prereqs: APhA NACDS MTM Elements

Key outputs: You should be able to choose CMR versus TMR from a board-style case, justify the choice using service scope and workflow rules, and document the pharmacist-appropriate next step.

Why it matters

  • BCMTMS questions often test not just what problem exists, but what level of MTM service is most appropriate for the pharmacist to deliver next.
  • Confusing CMR with TMR leads to wrong choices about time allocation, documentation, patient outputs, and follow-up planning.
  • In real practice, the distinction affects workflow design, outreach strategy, quality reporting, and how medication-related problems are prioritized.
  • On exam day, the winning move is usually to match the service to the scope of the problem: comprehensive for whole-regimen reassessment, targeted for a focused issue or trigger.

Key Terms & Must-Know Facts

Key terms

  • CMR: Comprehensive medication review of all medications and medication-related needs.
  • TMR: Targeted medication review focused on a specific problem, risk, gap, or trigger.
  • MTR: Medication therapy review; umbrella term that includes comprehensive and targeted reviews.
  • PMR: Personal medication record maintained for the patient.
  • MAP: Medication action plan written in patient-friendly language.
  • Medication-related problem: Issue involving indication, effectiveness, safety, adherence, access, or monitoring.
  • Problem-focused intervention: Narrow review addressing one or a few defined issues.
  • Longitudinal follow-up: Ongoing monitoring after the initial MTM encounter.
  • Transitions of care: Movement between care settings that can create discrepancies and urgent review needs.
  • Polypharmacy: Multiple concurrent medications increasing complexity and review needs.
  • Medication reconciliation: Verification of the most accurate medication list across sources.
  • Escalation: Directing urgent safety issues to emergency care or the appropriate clinician.

Must-know facts

  • CMR reviews the entire regimen; TMR reviews a specific issue.
  • CMR commonly produces or updates both a PMR and a MAP; TMR may not require both.
  • TMR is often episodic, trigger-based, and narrower in scope than CMR.
  • A patient can receive multiple TMRs over time between CMRs.
  • If the stem emphasizes one defined gap, risk, or discrepancy, think TMR first.
  • If the stem asks for reassessment of all medications, goals, adherence barriers, and overall regimen fit, think CMR.
  • TMR can uncover additional issues, but it does not automatically become a full CMR unless the case supports comprehensive reassessment.
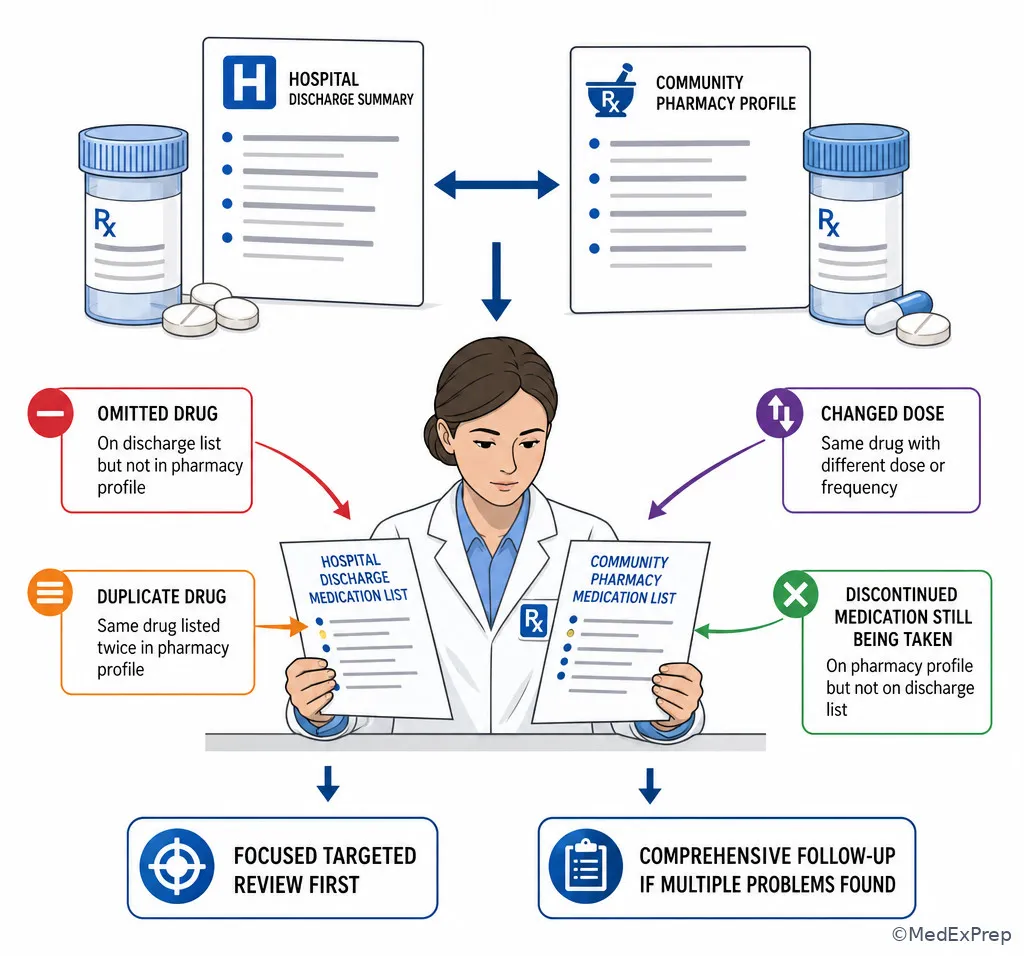
  • At transitions of care, pharmacist action often begins with reconciliation and focused triage; whether that becomes TMR or CMR depends on scope and workflow.
  • On the exam, choose the safest pharmacist action within scope: clarify, verify, recommend, document, follow up, or escalate.

Core content

Recall: In APhA NACDS MTM Elements, we covered the five core service elements: medication therapy review, PMR, MAP, intervention or referral, and documentation with follow-up. Here, we build on that by separating the broad umbrella term MTR into its two high-yield exam forms: CMR and TMR.
Fig 1. CMR versus TMR decision map
Exam takeaway: Match the breadth of the review to the breadth of the problem before choosing the MTM service.
flowchart TD
A[Start with the task] --> B{Is the question about all medications?}
B -->|Yes| C[CMR: full regimen review]
B -->|No| D{Is there a specific trigger or gap?}
D -->|Yes| E[TMR: focused review]
D -->|No| F{Recent major transition or major uncertainty?}
F -->|Yes| G[Clarify data and consider CMR if full reassessment is needed]
F -->|No| H[Use the narrowest safe pharmacist service that resolves the issue]
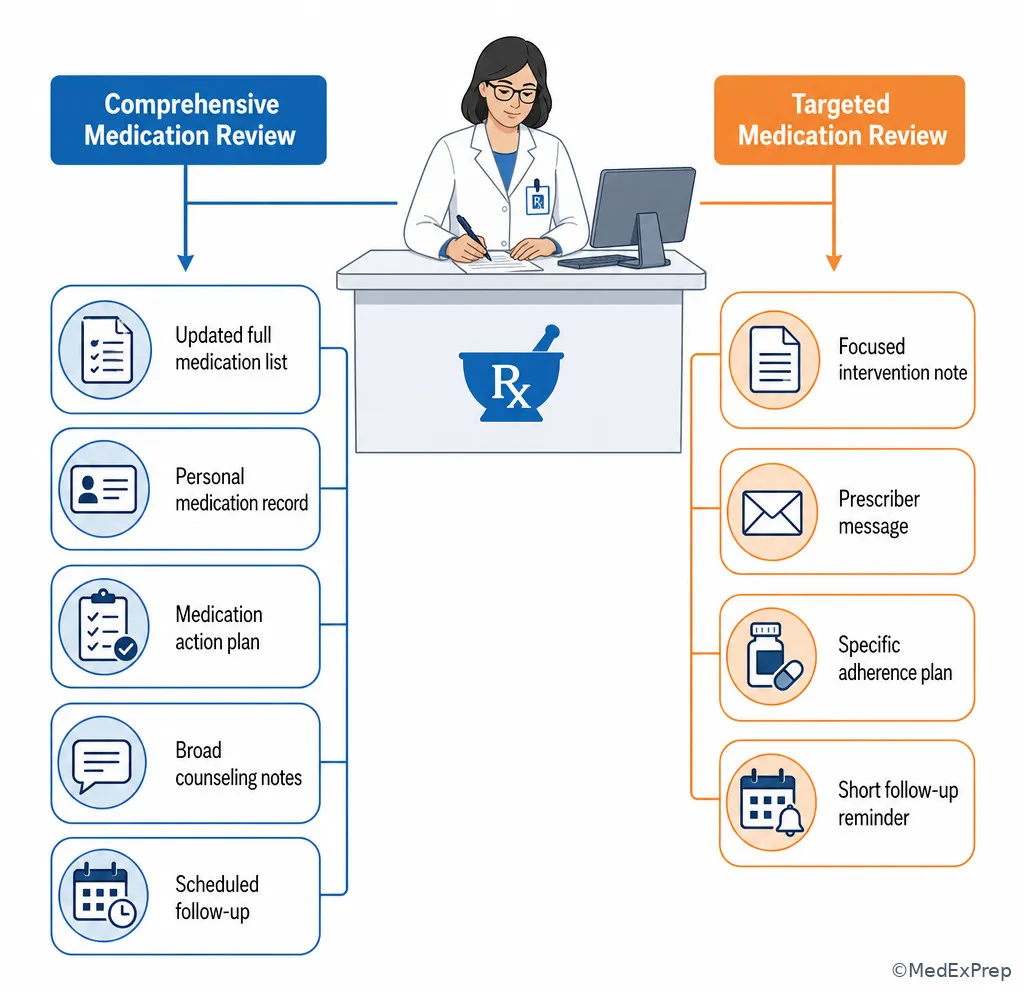
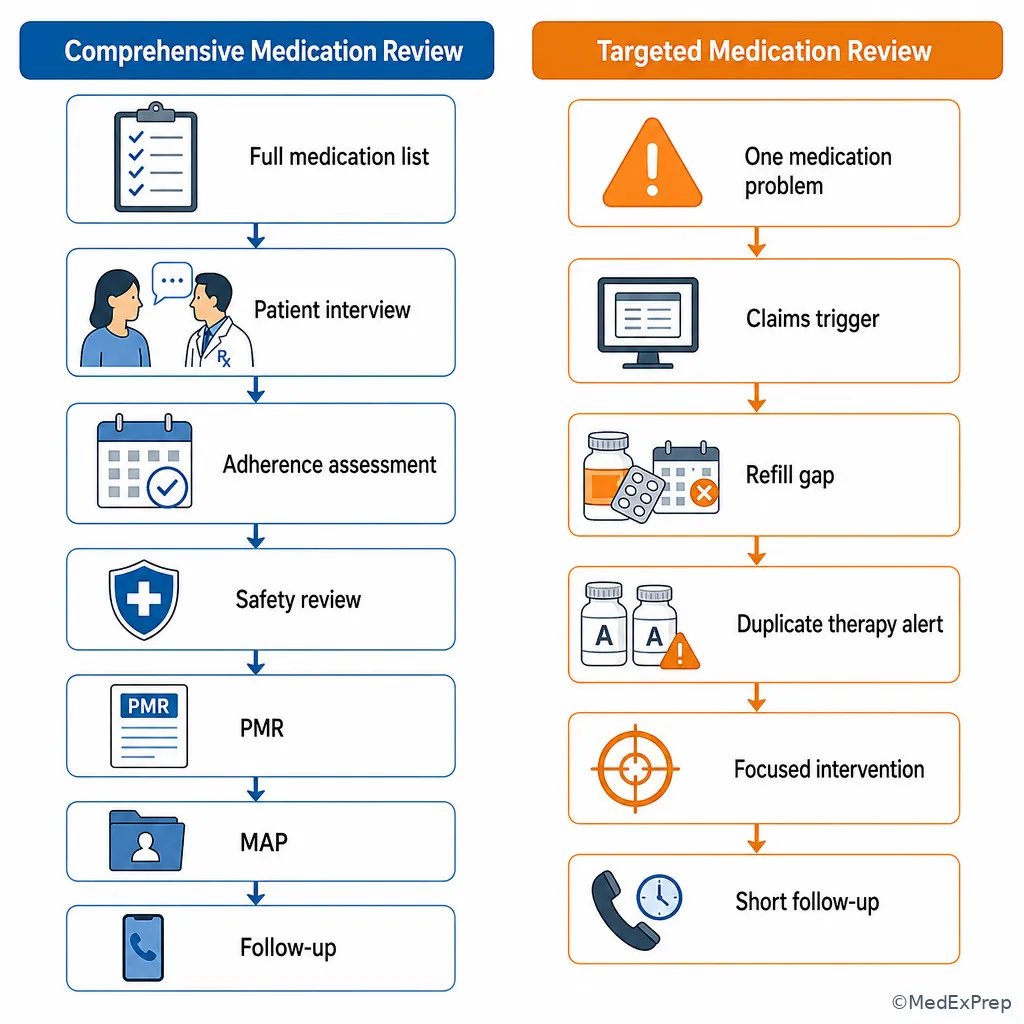
Workflow view of comprehensive versus targeted MTM
Exam takeaway: Visualize CMR as whole-regimen review and TMR as trigger-based focused follow-up.
Workflow view of comprehensive versus targeted MTM

1.1.2.1 Foundational distinction: what service are you actually choosing?

A. Explanation

The central decision conflict is simple: Do you need to review the patient's whole medication use experience, or do you need to solve one defined medication-related problem? That single choice resolves most exam stems. Choose CMR when the pharmacist must evaluate all prescription medications, OTC products, supplements, adherence patterns, safety risks, effectiveness, duplications, monitoring gaps, and patient goals across the full regimen. Choose TMR when the pharmacist is responding to a focused concern such as a refill adherence gap, high-risk drug alert, duplicate therapy flag, missing statin therapy in diabetes, post-discharge discrepancy, or a newly identified adverse effect.

WHY THIS IS TESTED: Board items often hide the answer by describing a problem list, a recent hospitalization, or a quality gap without directly naming the service. The testable pattern is whether the stem requires comprehensive reassessment or targeted intervention. If the question asks for the most appropriate next MTM service and gives only one drug issue, reject the temptation to overcall it a CMR just because the patient is complex. Complexity alone does not make every encounter comprehensive.

Think of CMR as a whole-chart medication optimization encounter and TMR as a focused maintenance or exception-management encounter. Both are under the MTR umbrella, but the expected deliverables differ. CMR is more likely to generate broad education, updated PMR, MAP, multiple problem identifications, and coordinated follow-up. TMR is more likely to produce a focused recommendation, clarification, triage, or monitoring plan around one issue.

Concept flow: Choose broad review versus focused intervention
Define the ask
Is the pharmacist being asked to assess the whole regimen or a single medication issue?

Decision
Whole regimen, multiple domains, broad goals → CMR. One trigger, one gap, one discrepancy → TMR.

Output
Match documentation, communication, and follow-up intensity to the chosen service.

Memory anchor: CMR = Complete picture; TMR = Triggered problem. If the stem is broad, go broad. If the stem is narrow, stay narrow.
Pharmacist Action: NOTICE: whether the stem points to all medications or one defined problem. SAY: "I want to review all of your medications together" for CMR, or "I want to focus on this specific medication concern" for TMR. MONITOR: completion of identified interventions and whether additional problems emerge. HOLD/CLARIFY/ESCALATE: clarify if the requested action exceeds pharmacist scope or if an urgent safety issue appears during either type of review.

B. Worked example

A 71-year-old woman with type 2 diabetes, hypertension, osteoarthritis, and stage 3 chronic kidney disease is referred to the MTM pharmacist. Her profile includes metformin 1000 mg by mouth twice daily, lisinopril 20 mg daily, hydrochlorothiazide 25 mg daily, atorvastatin 40 mg nightly, ibuprofen 400 mg three times daily as needed, omeprazole 20 mg daily, and several supplements. The referral note says she has not had a complete medication review in over a year, is confused about what she is still taking after seeing two specialists, and wants help understanding costs and side effects. A distracting detail is that her latest A1c improved from 8.9% to 7.1%.

Reasoning chain: Identify task: select the most appropriate MTM service. Extract key facts: overdue full review, multiple prescribers, confusion about the whole regimen, chronic diseases, supplements, and cost concerns. Apply rule: the problem is not one drug or one alert; it is whole-regimen reassessment. Eliminate distractors: a TMR would be too narrow because it would miss OTC-related safety issues, adherence misunderstandings, and global regimen cleanup. Verify: choose CMR because the pharmacist must assess indication, effectiveness, safety, adherence, and patient understanding across all therapies.

C. Exam trap

Common wrong answer: TMR. WHY IT IS TEMPTING: The patient has an obvious focused issue: NSAID use in CKD while taking lisinopril and hydrochlorothiazide. That is a real safety problem, so learners anchor on it and choose the narrower service. The SINGLE CLUE that eliminates it: the stem explicitly says she needs a complete medication review and is confused about her entire regimen after multiple specialist visits.

D. Checkpoint

Question: A 66-year-old man with atrial fibrillation, heart failure, and GERD takes apixaban 5 mg twice daily, metoprolol succinate 100 mg daily, furosemide 40 mg daily, potassium chloride 20 mEq daily, and pantoprazole 40 mg daily. During outreach, the pharmacist learns he was discharged 2 days ago and is unsure whether he should continue aspirin 81 mg daily that he used before admission. The most appropriate MTM service to address this immediate issue is:

  1. A. CMR
  2. B. TMR
  3. C. No MTM service; refer without review
  4. D. Delay review until the next annual outreach

Answer: B. TMR

  • A is tempting because post-discharge patients are often complex, but it is wrong here because the immediate question is a focused discrepancy about aspirin use, which fits a targeted review.
  • B is tempting because it matches the single post-discharge medication issue, and it is right because the pharmacist can perform a focused review, clarify discharge therapy, and communicate if needed.
  • C is tempting because discharge uncertainty may require prescriber contact, but it is wrong because pharmacist review is still appropriate before or while communicating the discrepancy.
  • D is tempting if one thinks CMR timing drives all MTM work, but it is wrong because potential duplicate antithrombotic risk needs prompt focused follow-up now.
If you missed this: Review 1.1.2.1 Foundational distinction: what service are you actually choosing? — focus on the rule that one defined discrepancy or trigger favors TMR even in a medically complex patient.

1.1.2.2 Service scope, triggers, and outputs

A. Explanation

The second decision conflict is not just what the service is called, but what work product should come out of it. Choose CMR when the service should produce broad outputs such as an updated medication list, patient education across the regimen, identification of several medication-related problems, and often a PMR and MAP. Choose TMR when the service output is a focused intervention: clarifying one drug, addressing one adherence barrier, resolving a discrepancy, checking a high-risk therapy, or responding to a population-health trigger.

WHY THIS IS TESTED: Exam writers often use output clues instead of definition clues. If the case asks what documentation element or patient-facing tool is most appropriate after the encounter, the answer often depends on whether the service was comprehensive or targeted. CMR is the classic setting for PMR and MAP production or update; TMR may still generate documentation and a recommendation, but its expected output is narrower and more issue-specific.

Typical CMR triggers include new enrollment into an MTM program, annual review timing, polypharmacy with multiple unresolved concerns, substantial regimen complexity, broad adherence concerns, multiple care transitions with list uncertainty, or a request for comprehensive reassessment. Typical TMR triggers include refill nonadherence flags, therapeutic duplication alerts, high-risk medication use, a care gap like missing statin therapy, one adverse effect concern, one drug-drug interaction, or a post-discharge discrepancy requiring rapid clarification.

On a board item, avoid over-reading payer details unless they are explicit. The safe exam move is not to infer a universal timing rule; instead, infer service type from the scope of the problem and the intended pharmacist action. See Fig 1.

Concept flow: Match triggers to outputs
Find the trigger
Annual full reassessment, complexity, and broad confusion suggest CMR; one alert or gap suggests TMR.

Select scope
Broad scope → full medication optimization. Narrow scope → focused problem resolution.

Deliver outputs
Choose PMR, MAP, recommendation, documentation, and follow-up intensity that fit the service.

Service element CMR TMR
Scope All medications and broad medication-use issues One or a few defined problems
Typical trigger Annual or first comprehensive review, major complexity Alert, gap, discrepancy, adherence issue, high-risk drug flag
Assessment breadth Indication, effectiveness, safety, adherence across full regimen Focused assessment tied to trigger
Patient outputs Often PMR and MAP updated or created Focused counseling or action item
Number of problems expected Often multiple Usually one or a limited set
Follow-up Planned longitudinal follow-up Short-interval issue-specific follow-up as needed
Fig 2. Trigger-to-service comparison
Exam takeaway: Use the trigger in the stem to predict whether the pharmacist should perform a comprehensive or focused review.
flowchart LR
A[Annual outreach or first full MTM encounter] --> B[CMR]
C[Multiple prescribers and whole-regimen confusion] --> B
D[Refill adherence gap on one medication] --> E[TMR]
F[High-risk drug alert or duplicate therapy] --> E
G[Post-discharge discrepancy involving one item] --> E
H[Need to reassess every medication, OTC, and supplement] --> B
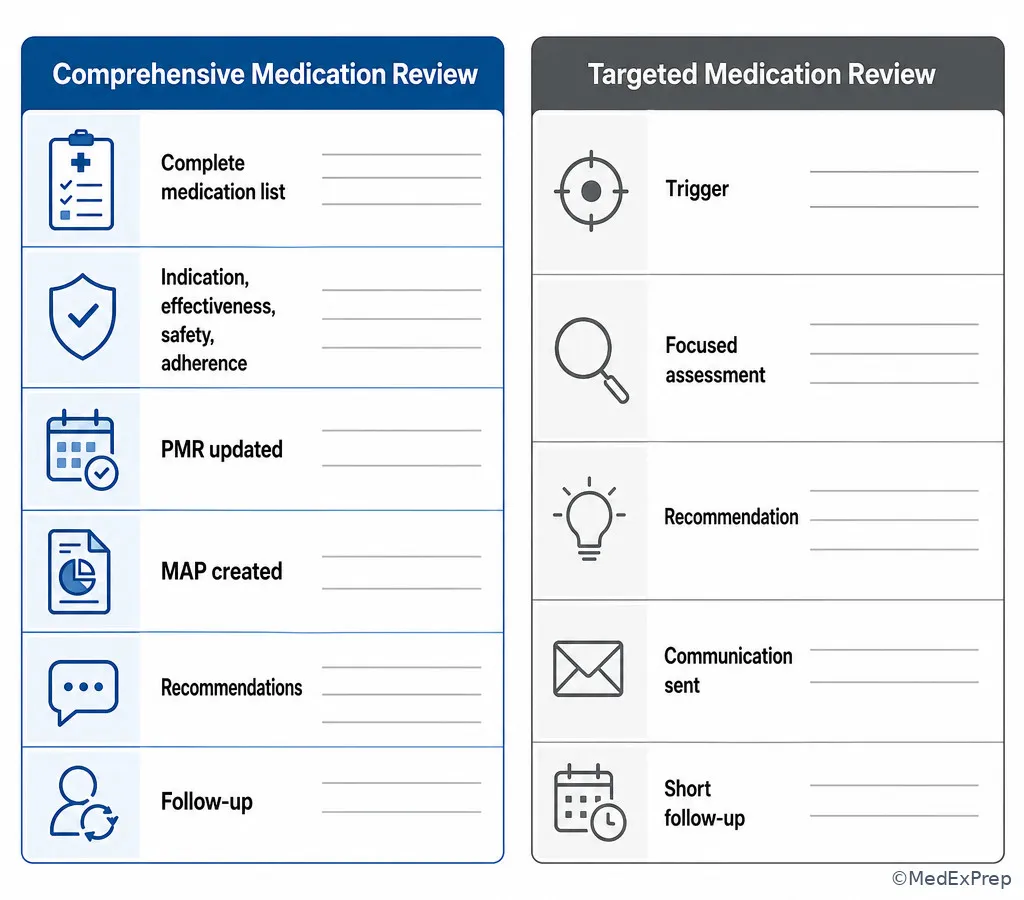
Patient-facing MTM outputs after different review types
Exam takeaway: CMR usually supports broad patient tools, while TMR usually supports a focused action or clarification.
Patient-facing MTM outputs after different review types

B. Worked example

A 59-year-old man with coronary artery disease, hyperlipidemia, and depression fills atorvastatin 80 mg nightly, clopidogrel 75 mg daily, sertraline 100 mg daily, and nitroglycerin as needed. A managed care dashboard flags a proportion-of-days-covered gap for atorvastatin over the past 60 days. He reports he stopped taking it because "my cholesterol looked good last visit," but he is otherwise adherent and recently completed a full annual medication review. A tempting wrong clue is that he also occasionally has leg cramps.

Reasoning chain: Identify task: choose service type and likely output. Extract key facts: one adherence gap, recent full review already done, otherwise stable regimen, focused medication issue. Apply rule: this is a TMR. Eliminate distractors: a new CMR is excessive because the problem is not full-regimen uncertainty. Verify: the likely output is focused adherence counseling, documentation of the statin gap, communication if needed, and short follow-up on refill persistence rather than a complete PMR/MAP rebuild.

C. Exam trap

Common wrong answer: CMR because the patient has cardiovascular disease and polypharmacy. WHY IT IS TEMPTING: High-risk disease states make broad review feel safer. The SINGLE CLUE that eliminates it: he recently completed a full annual review, and the current issue is a single statin adherence gap identified by population-health surveillance.

D. Checkpoint

Question: A pharmacist identifies a patient taking levothyroxine 75 mcg daily, calcium carbonate 1250 mg three times daily, and ferrous sulfate 325 mg daily. The patient says she takes all morning medications together and recently reported fatigue. The most appropriate MTM service classification for addressing this interaction-based adherence and administration issue is:

  1. A. TMR focused on the administration problem
  2. B. CMR because fatigue suggests a disease-state reassessment
  3. C. No review is needed if the prescriber ordered the regimen
  4. D. Delay until the next PMR update because the issue is educational only

Answer: A. TMR focused on the administration problem

  • A is tempting because it targets the identified timing interaction, and it is right because the pharmacist can address one clear medication-use problem without converting the encounter into a whole-regimen reassessment.
  • B is tempting because fatigue may reflect under-treated hypothyroidism, but it is wrong because the service classification is driven by the focused administration issue already identified.
  • C is tempting if one mistakes pharmacist scope as passive, but it is wrong because counseling on administration and interaction prevention is squarely within MTM practice.
  • D is tempting because the issue seems nonurgent, but it is wrong because the problem is ongoing and clinically relevant now.
If you missed this: Review 1.1.2.2 Service scope, triggers, and outputs — focus on using the trigger and intended work product to separate TMR from CMR.
Quick Recall:

  • The broad review that commonly updates a PMR and MAP is CMR.
  • True or False: A single refill gap after a recent annual review usually points to CMR. False.
  • Name the 3 fastest stem clues for TMR: single trigger, focused problem, narrow follow-up.
High-Yield Connection: This concept is tested alongside PMR and MAP Design. Know both the service type and the expected patient-facing outputs for exam day — they are frequently paired in stems.

1.1.2.3 Application in real MTM workflow: transitions, quality flags, and follow-up sequencing

A. Explanation

Now move from definitions to workflow. The decision conflict here is: Should the pharmacist use a focused intervention first, or schedule a comprehensive review now? The single rule is this: choose the narrowest safe service that addresses the immediate problem, but expand to CMR when the case reveals broad regimen uncertainty or multiple unresolved domains. In transitions of care, many cases begin as TMR because the first job is discrepancy resolution, medication reconciliation, or urgent safety triage. If that focused work uncovers widespread confusion, multiple duplications, or major gaps across the full regimen, a later or same-episode CMR may be warranted depending on workflow and authorization.

WHY THIS IS TESTED: The exam likes boundary cases. A patient may be recently discharged, have several chronic diseases, and still require only a focused TMR as the next step because one high-priority discrepancy must be solved first. Do not confuse eventual comprehensive care with the immediate best pharmacist action.

Population-health flags also push learners into overcalling CMR. If a dashboard reports missing statin therapy, suboptimal inhaler refill history, duplicate proton pump inhibitor use, or high-risk sedative exposure, the pharmacist often starts with TMR. The goal is to investigate the flagged issue, identify whether it is real, communicate recommendations, and decide whether a broader review should follow.

Sequencing matters. You may see patterns such as CMR followed by several TMRs, TMR after hospital discharge leading to later CMR, or TMR-only management when the issue remains focused. See Fig 2.

Concept flow: Sequence focused and comprehensive services
Start with the current risk
Resolve urgent discrepancy, interaction, or adherence issue first.

Decision
If the issue stays focused → continue TMR. If multiple regimen-wide issues emerge → schedule or convert to CMR.

Follow-up
Document what was resolved, what remains open, and the appropriate next review intensity.

Fig 3. Transition-of-care sequencing algorithm
Exam takeaway: In post-discharge stems, solve the immediate discrepancy first and expand to CMR only if the full regimen needs reassessment.
flowchart TD
A[Recent discharge or care transition] --> B[Reconcile medication list]
B --> C{One discrepancy or one urgent safety issue?}
C -->|Yes| D[TMR: focused clarification and communication]
C -->|No| E{Multiple unresolved medications, OTCs, and adherence barriers?}
E -->|Yes| F[CMR: comprehensive reassessment]
E -->|No| G[TMR now plus schedule broader follow-up if needed]
Common trigger Usually starts as When to escalate to broader review Typical pharmacist action
Post-discharge aspirin discrepancy TMR If full regimen confusion is uncovered Reconcile, clarify, document, communicate
Annual MTM outreach overdue CMR Not applicable; broad review already indicated Review complete regimen, update PMR/MAP
Refill gap for one chronic medication TMR If multiple adherence barriers across regimen emerge Investigate barrier, counsel, set follow-up
Duplicate therapy alert TMR If duplication is one of many list errors Verify active regimen and communicate recommendation
Multiple specialists and supplement use with confusion CMR Already broad by presentation Comprehensive medication assessment
Transitions-of-care medication reconciliation workflow
Exam takeaway: A recent discharge often starts with focused discrepancy resolution before a broader review is considered.
Transitions-of-care medication reconciliation workflow

B. Worked example

A 78-year-old man with heart failure, atrial fibrillation, diabetes, and mild cognitive impairment is contacted 4 days after discharge. He takes sacubitril/valsartan 49/51 mg twice daily, metoprolol succinate 50 mg daily, apixaban 5 mg twice daily, metformin 500 mg twice daily, and insulin glargine 20 units nightly. His daughter says he is taking both old lisinopril 20 mg daily and new sacubitril/valsartan because "the old doctor prescribed it first." A distracting detail is that his fasting glucose today was 178 mg/dL.

Reasoning chain: Identify task: choose the best pharmacist next service/action. Extract key facts: dangerous discharge discrepancy involving concurrent ACE inhibitor and ARNI, post-discharge context, one urgent medication safety problem. Apply rule: immediate focused intervention is priority. Eliminate distractors: although the patient is complex and may eventually need a CMR, the immediate service is best framed as TMR with urgent clarification and communication. Verify: pharmacist should reconcile, instruct not to continue unverified conflicting directions until clarified per local workflow, urgently communicate with the prescriber/team, document, and arrange follow-up.

C. Exam trap

Common wrong answer: Schedule CMR as the immediate next step. WHY IT IS TEMPTING: The patient is older, high risk, cognitively impaired, and has polypharmacy, all of which support comprehensive care. The SINGLE CLUE that eliminates it: there is a single urgent post-discharge safety discrepancy that must be clarified first.

D. Checkpoint

Question: A payer dashboard flags a 68-year-old woman with osteoporosis, GERD, and hypothyroidism for possible duplicate acid suppression therapy. She fills omeprazole 20 mg daily and pantoprazole 40 mg daily from different prescribers, completed a CMR 3 months ago, and denies other concerns. What is the most appropriate pharmacist MTM approach?

  1. A. Initiate another full CMR because duplicate therapy always requires comprehensive review
  2. B. Perform a TMR focused on duplicate therapy verification and recommendation
  3. C. Wait until the next annual review because the issue is not emergent
  4. D. Contact the patient only if both products are high-risk sedatives

Answer: B. Perform a TMR focused on duplicate therapy verification and recommendation

  • A is tempting because duplicate therapy can signal broader list problems, but it is wrong because the current trigger is one focused issue after a recent CMR.
  • B is tempting because it precisely matches the alert, and it is right because a focused review can verify active use and guide communication.
  • C is tempting because the issue may seem low urgency, but it is wrong because unnecessary duplicate therapy should be addressed once identified.
  • D is tempting because higher-risk classes may demand urgency, but it is wrong because duplicate PPIs still warrant focused review and intervention.
If you missed this: Review 1.1.2.3 Application in real MTM workflow: transitions, quality flags, and follow-up sequencing — focus on choosing the narrowest safe next step before expanding to CMR.
Pharmacist Action: NOTICE: whether the trigger is urgent, focused, and actionable now. SAY: "I need to verify this medication discrepancy first so we can prevent harm." MONITOR: issue resolution within days for transitions or high-risk alerts; broader follow-up later if needed. HOLD/CLARIFY/ESCALATE: escalate immediately for red-flag symptoms, dangerous interactions, toxicities, or unclear discharge instructions with significant harm potential.

1.1.2.4 Documentation and communication: what must be recorded for each service?

A. Explanation

The next decision conflict is: How much documentation is necessary, and what communication should the pharmacist include? The single rule is to document enough to defend the service actually performed. For CMR, documentation should reflect comprehensive assessment across the medication list, identified medication-related problems, patient education, PMR and MAP status, recommendations, and planned follow-up. For TMR, documentation should clearly state the focused trigger, the assessment tied to that issue, the recommendation or counseling provided, communication with the care team if applicable, and how resolution will be checked.

WHY THIS IS TESTED: Examiners know learners memorize definitions but forget operational details. A question may ask for the best documentation element after a focused adherence outreach or which communication is most appropriate after a comprehensive review. The answer hinges on whether the service was comprehensive or targeted. Under-documenting a CMR makes it look like a TMR; over-documenting a TMR as if it were a full review wastes workflow and misses the exam distinction.

Use a consistent pharmacist reasoning frame: identify the problem category, note the evidence supporting it, state the action taken or recommendation made, identify who was notified, and specify follow-up timing. In CMR documentation, make it clear that all medications were considered. In TMR documentation, make it clear why the review was focused and what narrowed the scope. See Fig 3.

Concept flow: Document the service you actually delivered
Name the service
State whether the encounter was comprehensive or targeted.

Match content to scope
CMR documents full-regimen assessment; TMR documents the trigger, focused assessment, and action.

Close the loop
Record communication, patient understanding, monitoring plan, and follow-up date or threshold.

Documentation component CMR emphasis TMR emphasis
Reason for encounter Comprehensive medication assessment Specific trigger or problem
Medication list review Entire regimen including OTCs and supplements Focused list elements relevant to the issue
Assessment domains Indication, effectiveness, safety, adherence broadly Focused domain linked to trigger
Patient tools PMR and MAP often updated Issue-specific education or instructions
Care team communication May include several recommendations Usually one focused recommendation or clarification
Follow-up Broad scheduled reassessment Short-interval check on focused issue
Fig 4. Documentation framework for CMR and TMR
Exam takeaway: Document the trigger, scope, action, communication, and follow-up in a way that proves whether the service was comprehensive or targeted.
flowchart TD
A[Encounter occurs] --> B{CMR or TMR?}
B -->|CMR| C[Document full medication list review]
C --> D[Record multiple problems and PMR/MAP status]
D --> E[Plan broad follow-up]
B -->|TMR| F[Document the focused trigger]
F --> G[Record issue-specific assessment and intervention]
G --> H[Plan focused follow-up and communication]
MTM documentation layout for focused versus comprehensive notes
Exam takeaway: Note structure should mirror service scope so another clinician can understand what was reviewed and what remains open.
MTM documentation layout for focused versus comprehensive notes

B. Worked example

A 64-year-old woman with rheumatoid arthritis, hypertension, and chronic insomnia takes methotrexate 15 mg weekly, folic acid 1 mg daily, amlodipine 10 mg daily, zolpidem 10 mg nightly, and several OTC products. During a recent CMR, the pharmacist identified multiple concerns and updated the PMR and MAP. Two weeks later, refill data show poor adherence to folic acid only. The pharmacist contacts the patient and learns she thought folic acid was optional. A tempting but wrong clue is that she also reports occasional dizziness from zolpidem.

Reasoning chain: Identify task: choose the correct documentation level for the new encounter. Extract key facts: prior CMR already completed, current issue is isolated to one supportive medication, intervention is focused counseling. Apply rule: document this as a TMR linked to the folic acid adherence problem, not a repeat comprehensive note. Eliminate distractors: mentioning every old CMR issue again would blur service boundaries. Verify: the note should record the trigger, the misunderstanding, counseling provided, adherence plan, and follow-up to verify refill completion.

C. Exam trap

Common wrong answer: Re-document the whole regimen because comprehensive notes are more complete. WHY IT IS TEMPTING: Learners equate more detail with better documentation. The SINGLE CLUE that eliminates it: this encounter addressed one new, focused issue after a recent CMR, so the documentation should match a TMR.

D. Checkpoint

Question: After a focused review of nonadherence to rosuvastatin 20 mg nightly in a patient with diabetes and ASCVD, which documentation element most strongly supports that the pharmacist performed a TMR rather than a CMR?

  1. A. A statement that the pharmacist updated every OTC and supplement in the record and reassessed all medication-related problems
  2. B. A note that the trigger was a refill gap, the patient stopped due to myalgias, counseling was provided, and follow-up was planned in 2 weeks
  3. C. A full annual PMR and MAP with broad lifestyle education across all conditions
  4. D. A generalized note that "medications reviewed" with no specific issue documented

Answer: B. A note that the trigger was a refill gap, the patient stopped due to myalgias, counseling was provided, and follow-up was planned in 2 weeks

  • A is tempting because it sounds thorough, but it is wrong because it describes full-regimen reassessment more consistent with CMR.
  • B is tempting because it centers on one trigger, and it is right because targeted documentation should state the issue, action, and focused follow-up.
  • C is tempting because PMR and MAP are valuable outputs, but it is wrong because those broad outputs align more strongly with CMR.
  • D is tempting because it seems brief and efficient, but it is wrong because it does not defensibly document the problem-focused nature of the service.
If you missed this: Review 1.1.2.4 Documentation and communication: what must be recorded for each service? — focus on documenting the trigger and scope so the note proves a TMR versus a CMR.
Quick Recall:

  • The note element that most clearly marks a TMR is the specific trigger.
  • True or False: A broad PMR and MAP update is most associated with TMR. False.
  • Name the 3 close-the-loop items after either service: communication, follow-up, patient understanding.
High-Yield Connection: This concept overlaps with Defensible MTM Documentation and SBAR SOAP And Counseling. Know both service selection and note structure — exam stems often test them together.
Pharmacist Action: NOTICE: whether your documentation matches the actual scope reviewed. SAY: "Today we focused on this one medication concern" for TMR or "We reviewed your full medication regimen" for CMR. MONITOR: whether recommendations were communicated and accepted, plus the issue-specific outcome or broad follow-up goal. HOLD/CLARIFY/ESCALATE: clarify missing discharge data, conflicting lists, or unsafe directions before closing the note.

1.1.2.5 Integration: common boundary cases and how to choose safely on exam day

A. Explanation

The final decision conflict is the hardest one: What if the patient is globally complex, but the stem asks about one immediate task? The single rule is to answer the question asked, not the broader care the patient may eventually need. If the stem asks for the most appropriate next MTM step and presents one pressing discrepancy, one refill gap, one counseling issue, or one monitoring problem, choose TMR unless the wording clearly requires comprehensive reassessment. If the stem asks what service best addresses medication complexity, multiple uncontrolled conditions, widespread misunderstanding, broad OTC or supplement use, or need for regimen-wide optimization, choose CMR.

WHY THIS IS TESTED: Exam writers build noise into cases. They add age, comorbidities, many medications, and a tempting broad-service cue even when the actual decision is focused. Your task is to separate background complexity from the active decision node.

Boundary cases often include: a recent CMR with a new alert, a TMR that reveals multiple hidden problems, a transition-of-care case with one dangerous discrepancy but likely additional issues, or a quality report identifying one care gap in an otherwise stable patient. In each case, ask two questions: What is the immediate highest-priority medication-related problem? and Does resolving it require a whole-regimen review right now? If no, choose TMR. If yes, choose CMR. See Fig 4.

Finally, remember pharmacist scope. If a focused review reveals urgent symptoms, dangerous interactions, or severe adverse effects, your role is not to independently diagnose; it is to recognize risk, communicate clearly, and escalate appropriately. Service type does not override safety.

Concept flow: Handle boundary cases without overcalling CMR
Find the immediate problem
Prioritize the medication issue the stem wants solved now.

Decision
If one issue can be safely addressed in isolation → TMR. If the answer needs regimen-wide reassessment → CMR.

Protect scope and safety
Clarify, recommend, or escalate instead of acting beyond authorization.

Fig 5. Boundary-case exam stem anatomy
Exam takeaway: Ignore background noise and choose the service based on the immediate medication-related problem the pharmacist must address.
Fig 5. Boundary-case exam stem anatomy
Service selection ladder from focused issue to comprehensive review
Exam takeaway: A targeted issue can stay targeted unless multiple unresolved problems force expansion to full-regimen review.
Service selection ladder from focused issue to comprehensive review

B. Worked example

A 73-year-old woman with COPD, type 2 diabetes, coronary artery disease, and chronic pain takes tiotropium inhaled daily, albuterol as needed, metformin 1000 mg twice daily, empagliflozin 10 mg daily, aspirin 81 mg daily, rosuvastatin 20 mg nightly, and tramadol 50 mg every 8 hours as needed. She had a CMR 5 months ago. The pharmacy system now flags poor refill history for tiotropium. When contacted, she says she stopped it because it "didn't work right away," but also mentions she never understood how to use the inhaler. A distracting detail is that she had mild nausea after starting empagliflozin months ago.

Reasoning chain: Identify task: most appropriate next MTM step. Extract key facts: recent CMR, one current adherence and technique problem tied to one medication, no evidence of broad regimen confusion. Apply rule: this is TMR. Eliminate distractors: the chronic pain medication and SGLT2 adverse-effect history are noise in this stem. Verify: focused inhaler counseling, adherence barrier assessment, technique education, documentation, and follow-up are the correct targeted actions. A future CMR may still occur later, but it is not the next best answer.

C. Exam trap

Common wrong answer: CMR because the patient has several chronic conditions and polypharmacy. WHY IT IS TEMPTING: Complex patients often do benefit from comprehensive reviews. The SINGLE CLUE that eliminates it: the case presents one active, clearly defined inhaler-use and adherence problem after a recent CMR.

D. Checkpoint

Question: A 62-year-old man with hypertension, gout, and depression takes losartan 100 mg daily, allopurinol 300 mg daily, sertraline 50 mg daily, and naproxen 500 mg twice daily as needed. He completed a CMR 1 month ago. Today he calls because a new urgent care clinician added indomethacin 50 mg three times daily for gout and he asks whether he should take both NSAIDs. What is the most appropriate pharmacist MTM service framing?

  1. A. CMR, because any new prescription after a CMR requires a complete new review
  2. B. TMR, because the pharmacist needs to address one focused duplicate NSAID safety question
  3. C. No MTM intervention; advise the patient to choose based on pain severity
  4. D. Delay all discussion until the prescriber can complete a full disease reassessment

Answer: B. TMR, because the pharmacist needs to address one focused duplicate NSAID safety question

  • A is tempting because a new drug can affect the whole regimen, but it is wrong because the immediate decision is a narrow safety clarification.
  • B is tempting because it targets one high-yield medication-related problem, and it is right because focused review is sufficient for the question asked.
  • C is tempting if one underestimates the pharmacist role, but it is wrong because duplicate NSAID exposure warrants pharmacist counseling and likely prescriber communication.
  • D is tempting because gout treatment belongs to the prescriber, but it is wrong because the pharmacist should still address the immediate medication safety issue now.
If you missed this: Review 1.1.2.5 Integration: common boundary cases and how to choose safely on exam day — focus on answering the immediate task in the stem rather than the broader care the patient may eventually need.
Memory anchor: For boundary stems, use NARROW first: Notice the active problem, Answer the next-step question, Reject background noise, Resolve focused risk, Only expand if whole-regimen review is needed, Write the right documentation.
Pharmacist Action: NOTICE: whether the stem asks for the next best focused step or broad ongoing management. SAY: "I can address this medication safety question now and coordinate with your prescriber if needed." MONITOR: resolution of the targeted issue and whether additional unresolved regimen problems surface. HOLD/CLARIFY/ESCALATE: escalate red flags such as severe adverse effects, bleeding, dyspnea, or signs of toxicity regardless of service type.

Exam Traps & Differentiators

Most common wrong answer and why: Choosing CMR whenever a patient has many diseases or many medications. This is tempting because complexity feels like it should always trigger a broad review. The discriminator is the scope of the active task, not the total number of medications alone.

Looks similar Actually think Single discriminator
Complex patient with one refill gap TMR One defined adherence problem after prior comprehensive review
Post-discharge patient with one discrepancy TMR first Immediate focused clarification is the next best step
Patient confused about every medication after multiple prescribers CMR Whole-regimen uncertainty
Need to update PMR and MAP for the full regimen CMR Broad patient-facing outputs across all medications
Quality dashboard alert on duplicate therapy TMR Single focused trigger unless broader problems emerge
One adverse effect complaint during routine outreach TMR Issue-specific safety review
  • If the stem says "annual review," "complete medication review," or "review all medications including OTCs and supplements," think CMR.
  • If the stem says "refill gap," "high-risk alert," "duplicate therapy," or "one discrepancy," think TMR.
  • If the stem says "recent CMR completed" plus a new isolated issue, think TMR.
  • If the stem says "confused about what to take after seeing multiple clinicians," think CMR unless one urgent issue clearly takes priority first.
  • If the stem says "most appropriate next step" in a transition case, think focused reconciliation and triage before broad reassessment.
Common traps & distractors: In neighboring topics, PMR and MAP Design can create a confusable pair: learners may assume every MTM encounter requires a full PMR and MAP refresh. That is too broad. CMR most strongly supports those whole-regimen patient tools, while TMR may only require issue-specific education and documentation.
Review connection: The traps above test service-scope matching. If any felt unfamiliar, revisit 1.1.2.2 Service scope, triggers, and outputs before attempting the Self-check quiz.

Algorithm / Approach

Fig 6. Exam-day algorithm for choosing CMR versus TMR
Exam takeaway: Start with the immediate problem and expand only when the case clearly requires whole-regimen reassessment.
flowchart TD
A[Read the stem] --> B[Find the medication context and pharmacist task]
B --> C{Does the pharmacist need to assess all medications, OTCs, adherence, safety, and goals?}
C -->|Yes| D[Choose CMR]
C -->|No| E{Is there one specific trigger, discrepancy, alert, or gap?}
E -->|Yes| F[Choose TMR]
E -->|No| G{Did the focused issue uncover broad regimen confusion or multiple open problems?}
G -->|Yes| H[Escalate to or schedule CMR]
G -->|No| I[Stay with TMR and close the loop]
D --> J[Document comprehensive findings, PMR/MAP status, recommendations, follow-up]
F --> K[Document trigger, focused assessment, action, communication, follow-up]
H --> J
I --> K
Concept flow: Five-step pharmacist decision framework
Identify task
What is the pharmacist being asked to do right now?

Extract scope clues
Look for whole-regimen language versus one focused trigger.

Choose service
Broad reassessment → CMR. Focused issue → TMR.

Act within scope
Clarify, recommend, counsel, document, or escalate.

Close the loop
Plan focused or comprehensive follow-up based on what remains unresolved.

Use this algorithm when the stem feels noisy. First, identify whether the pharmacist's task is broad or narrow. Second, anchor on the immediate medication-related problem, not the patient's entire medical history. Third, choose the least expansive service that safely resolves the problem. Fourth, document and communicate in proportion to that service. Fifth, if the targeted review exposes several unresolved issues, convert or schedule a later CMR rather than pretending the initial focused interaction was comprehensive.

Rapid Review

  • CMR → full-regimen assessment across indication, effectiveness, safety, and adherence
  • TMR → focused response to one trigger, gap, discrepancy, or alert
  • Recent annual review + new isolated problem → TMR
  • Multiple prescribers + broad regimen confusion → CMR
  • Post-discharge one dangerous discrepancy → TMR first
  • Need to update PMR and MAP for the full regimen → think CMR
  • Refill adherence flag on one chronic medication → think TMR
  • Complexity alone → not enough to force CMR
  • Question asks for "most appropriate next step" → solve the active issue first
  • TMR may uncover broader issues → schedule or escalate to CMR if needed
  • Documentation must prove service scope → trigger for TMR, full list review for CMR
  • Pharmacist scope in either service → clarify, recommend, document, follow up, escalate when unsafe

Self-check quiz

1. A pharmacist reviews a patient taking atorvastatin 40 mg nightly, metformin 1000 mg twice daily, lisinopril 20 mg daily, and aspirin 81 mg daily. The referral specifically asks for a review of all prescription medications, OTC products, adherence barriers, and patient goals because no full MTM encounter has occurred in 18 months. What is the most appropriate MTM service?

  1. A. CMR
  2. B. TMR
  3. C. Focused refill synchronization visit
  4. D. Adverse-effect hotline triage only

2. A patient taking rosuvastatin 20 mg nightly, ezetimibe 10 mg daily, and amlodipine 5 mg daily completed a CMR 2 months ago. A claims report now shows a refill gap only for rosuvastatin. Which MTM service is most appropriate for the pharmacist to perform next?

  1. A. CMR
  2. B. TMR
  3. C. Annual PMR rebuild without patient contact
  4. D. No MTM activity until year-end

3. A 74-year-old man with heart failure and atrial fibrillation takes apixaban 5 mg twice daily, metoprolol succinate 50 mg daily, furosemide 40 mg daily, and pantoprazole 40 mg daily. He was discharged yesterday and asks whether he should continue old aspirin 81 mg daily found in his pillbox. He also mentions mild constipation. What is the most appropriate pharmacist MTM service framing?

  1. A. Immediate CMR because he has multiple cardiovascular medications
  2. B. TMR focused on the antithrombotic discrepancy
  3. C. No review; the pharmacist should wait for the cardiologist to diagnose the issue
  4. D. Delay all intervention until a new PMR can be mailed

4. A 61-year-old woman with hypothyroidism, osteopenia, and iron-deficiency anemia takes levothyroxine 88 mcg every morning, calcium citrate 600 mg twice daily, and ferrous sulfate 325 mg daily. She completed a CMR 4 months ago. During follow-up, she reports taking all three together before breakfast because it is easier. What is the most appropriate pharmacist service?

  1. A. CMR because the regimen includes supplements and a chronic disease
  2. B. TMR because the issue is a focused administration and interaction problem
  3. C. Emergency escalation because fatigue may indicate uncontrolled hypothyroidism
  4. D. No intervention because administration timing is not a medication-related problem

5. A managed care pharmacist reviews a patient taking tiotropium inhaled daily, albuterol as needed, metformin 500 mg twice daily, and losartan 50 mg daily. The patient completed a comprehensive review 3 months ago, but refill history now suggests poor persistence with tiotropium. The patient says the inhaler "never seemed to help" and admits not understanding the inhalation steps. What is the most appropriate next service?

  1. A. TMR focused on inhaler adherence and technique
  2. B. CMR because inhaler misuse may indicate poor self-management overall
  3. C. Annual CMR scheduling only, with no current intervention
  4. D. Recommend switching inhalers independently without further review

6. A 79-year-old woman with CKD, diabetes, and osteoarthritis takes metformin 500 mg twice daily, lisinopril 10 mg daily, hydrochlorothiazide 25 mg daily, ibuprofen 400 mg three times daily as needed, and omeprazole 20 mg daily. She has not had an MTM encounter in more than a year, reports using several supplements from memory, and says two specialists changed medications recently. The referral note specifically asks the pharmacist to address NSAID safety. Which service is most appropriate as the best overall next step?

  1. A. TMR because the referral names one drug-safety concern
  2. B. CMR because the stem reveals broad regimen uncertainty beyond the single referral issue
  3. C. No MTM service; only the nephrologist should evaluate this case
  4. D. Delay until laboratory results are available because MTM cannot proceed without them

7. A 68-year-old man with coronary artery disease, diabetes, and GERD takes clopidogrel 75 mg daily, atorvastatin 80 mg nightly, metformin 1000 mg twice daily, and pantoprazole 40 mg daily. He had a CMR 6 weeks ago. Today a duplicate acid suppression alert appears because omeprazole 20 mg daily was filled at an outside pharmacy. He denies other medication concerns and wants to know which acid suppressant to continue. What is the most appropriate MTM service classification?

  1. A. CMR because duplicate therapy can affect the entire medication list
  2. B. TMR because the current problem is a focused duplicate therapy clarification after a recent CMR
  3. C. No review because GI therapy is outside MTM scope
  4. D. Emergency referral because duplicate PPI use is inherently emergent

8. A 72-year-old woman with heart failure, depression, and chronic insomnia takes sacubitril/valsartan 49/51 mg twice daily, metoprolol succinate 100 mg daily, sertraline 100 mg daily, and zolpidem 10 mg nightly. She completed a CMR 2 months ago. During a targeted outreach for delayed refill of sertraline, the pharmacist learns she also restarted an old bottle of lisinopril 20 mg daily after reading a prior medication list and is now unsure which cardiac medicines are current. What is the most appropriate pharmacist next step?

  1. A. Continue the planned TMR only and ignore the cardiac issue because it was outside the original trigger
  2. B. Address the urgent discrepancy immediately, document focused intervention, and determine whether broader follow-up or CMR is needed
  3. C. Perform no intervention until the next annual CMR because one is already on file
  4. D. Independently discontinue lisinopril in the record without clarifying with the patient or prescriber

Answer key

1. Correct answer: A. CMR

  • A. CMR: Tempting because the stem explicitly asks for a broad medication assessment, and correct because the patient needs review of all drugs, OTCs, adherence barriers, and goals across the full regimen. The single discriminating clue is "no full MTM encounter has occurred in 18 months" plus comprehensive scope language. This aligns with MTM core elements described by APhA/NACDS and standard MTM frameworks. Sources: APhA/NACDS MTM service model; DiPiro.
  • B. TMR: Tempting because one could focus on any individual chronic drug, but incorrect because the stem requires comprehensive reassessment rather than a single trigger response. The eliminating fact is the explicit request to review all medications. Sources: APhA/NACDS; ACCP MTM practice principles.
  • C. Focused refill synchronization visit: Tempting because adherence support is part of MTM, but incorrect because synchronization does not replace the broad service requested. The eliminating clue is the need for global medication and goal review. Sources: APhA/NACDS.
  • D. Adverse-effect hotline triage only: Tempting if one narrows the case to safety, but incorrect because no isolated adverse-effect complaint defines the encounter. The discriminating clue is comprehensive MTM outreach. Sources: DiPiro; APhA/NACDS.
If you missed this: Review 1.1.2.1 Foundational distinction: what service are you actually choosing? — focus on the rule that whole-regimen language points to CMR.

2. Correct answer: B. TMR

  • A. CMR: Tempting because statin adherence is clinically important, but incorrect because a recent CMR already occurred and the current issue is a single refill gap. The discriminating clue is "completed a CMR 2 months ago." Sources: APhA/NACDS; ASHP ambulatory care practice standards.
  • B. TMR: Tempting because it precisely matches the focused refill trigger, and correct because a targeted review is appropriate for one identified adherence gap. The single clue is the isolated rosuvastatin nonpersistence. Sources: APhA/NACDS; managed care MTM workflow principles.
  • C. Annual PMR rebuild without patient contact: Tempting because documentation updates matter, but incorrect because the immediate need is patient-specific intervention on adherence, not passive record maintenance. The eliminating clue is active refill nonadherence. Sources: APhA/NACDS.
  • D. No MTM activity until year-end: Tempting if one confuses CMR timing with all MTM work, but incorrect because TMR can occur between CMRs when focused issues arise. The discriminating fact is episodic targeted review. Sources: APhA/NACDS; DiPiro.
If you missed this: Review 1.1.2.2 Service scope, triggers, and outputs — focus on the rule that a refill-gap trigger after recent comprehensive review favors TMR.

3. Correct answer: B. TMR focused on the antithrombotic discrepancy

  • A. Immediate CMR because he has multiple cardiovascular medications: Tempting because cardiovascular polypharmacy raises overall risk, but incorrect because the next best action is to clarify one high-priority discrepancy. The single clue is uncertainty about continuing old aspirin after discharge. Sources: APhA/NACDS; ASHP transitions-of-care guidance.
  • B. TMR focused on the antithrombotic discrepancy: Tempting because it targets the urgent medication safety issue, and correct because focused discrepancy resolution is the immediate pharmacist role. The discriminating clue is recent discharge with one clear aspirin question. Sources: ASHP transitions-of-care; APhA/NACDS.
  • C. No review; wait for the cardiologist to diagnose: Tempting because prescriber confirmation may be needed, but incorrect because the pharmacist should still perform reconciliation, clarify records, counsel, and communicate. The eliminating fact is that medication review is within pharmacist scope. Sources: ASHP; ACCP practice guidance.
  • D. Delay all intervention until a new PMR can be mailed: Tempting because patient-facing tools matter, but incorrect because potential duplicate antithrombotic exposure should not wait for administrative steps. The discriminating clue is immediate safety relevance. Sources: APhA/NACDS.
If you missed this: Review 1.1.2.3 Application in real MTM workflow: transitions, quality flags, and follow-up sequencing — focus on solving the immediate discrepancy first in post-discharge stems.

4. Correct answer: B. TMR because the issue is a focused administration and interaction problem

  • A. CMR because the regimen includes supplements and a chronic disease: Tempting because supplements often complicate medication review, but incorrect because the active problem is one administration interaction after a recent CMR. The discriminating clue is that all three are being taken together. Sources: Lexicomp administration guidance; APhA/NACDS.
  • B. TMR because the issue is a focused administration and interaction problem: Tempting because it matches the immediate counseling need, and correct because targeted review is sufficient to address levothyroxine interaction timing. The single clue is focused administration error with prior comprehensive review completed. Sources: Lexicomp; Clinical Pharmacology; APhA/NACDS.
  • C. Emergency escalation because fatigue may indicate uncontrolled hypothyroidism: Tempting because symptoms matter, but incorrect because fatigue alone in this context does not demand emergency referral; the medication-use problem is the first pharmacist target. The eliminating clue is the clear timing interaction without red-flag emergency symptoms. Sources: Lexicomp; DiPiro.
  • D. No intervention because administration timing is not a medication-related problem: Tempting if one underestimates counseling, but incorrect because improper timing affects absorption and treatment effectiveness. The single eliminator is the PK interaction with calcium and iron. Sources: Lexicomp; FDA labeling.
If you missed this: Review 1.1.2.2 Service scope, triggers, and outputs — focus on the rule that one administration or interaction problem is a TMR trigger.

5. Correct answer: A. TMR focused on inhaler adherence and technique

  • A. TMR focused on inhaler adherence and technique: Tempting because it directly addresses one drug-specific barrier, and correct because the patient had a recent CMR and now has a single inhaler-use problem. The discriminating clue is poor persistence tied to misunderstanding inhalation steps. Sources: APhA/NACDS; guideline-based inhaler education principles in DiPiro.
  • B. CMR because inhaler misuse may indicate poor self-management overall: Tempting because technique problems can reflect broader needs, but incorrect because the question asks for the most appropriate next service for the identified issue. The eliminating clue is recent comprehensive review plus isolated tiotropium problem. Sources: APhA/NACDS.
  • C. Annual CMR scheduling only, with no current intervention: Tempting because annual reviews are part of MTM structure, but incorrect because an active adherence barrier needs current action. The discriminating clue is actionable inhaler misuse now. Sources: APhA/NACDS.
  • D. Recommend switching inhalers independently without further review: Tempting because lack of perceived benefit may suggest product mismatch, but incorrect because independent therapy change may exceed scope when not authorized, and technique should be assessed first. The eliminator is the patient's admission of not understanding use. Sources: APhA/NACDS; pharmacist scope guardrails.
If you missed this: Review 1.1.2.5 Integration: common boundary cases and how to choose safely on exam day — focus on ignoring complexity noise when one current medication problem drives the next step.

6. Correct answer: B. CMR because the stem reveals broad regimen uncertainty beyond the single referral issue

  • A. TMR because the referral names one drug-safety concern: Tempting because ibuprofen in CKD while using lisinopril and hydrochlorothiazide is a focused safety problem, but incorrect because the stem adds overdue MTM, supplements not clearly known, multiple specialist changes, and broad uncertainty. The single clue that discriminates is whole-regimen confusion beyond the referral label. Sources: APhA/NACDS; DiPiro.
  • B. CMR because the stem reveals broad regimen uncertainty beyond the single referral issue: Tempting because it may feel "too big" for one question, and correct because the pharmacist needs assessment across all medications, OTCs, and supplements. The discriminating clue is no MTM encounter for over a year plus medication changes by multiple specialists. Sources: APhA/NACDS; ACCP medication management principles.
  • C. No MTM service; only the nephrologist should evaluate this case: Tempting because CKD adds complexity, but incorrect because pharmacist-led comprehensive medication review is within scope, with recommendations and communication as needed. The eliminating fact is that identifying safety and regimen problems is core MTM work. Sources: ACCP; APhA/NACDS.
  • D. Delay until laboratory results are available because MTM cannot proceed without them: Tempting because labs help assess safety, but incorrect because a CMR can still begin with available data while additional information is gathered. The discriminating clue is broad medication confusion requiring review now. Sources: APhA/NACDS; ASHP practice standards.
If you missed this: Review 1.1.2.1 Foundational distinction: what service are you actually choosing? — focus on the discriminator that a named referral issue does not prevent CMR when the rest of the stem clearly requires whole-regimen reassessment.

7. Correct answer: B. TMR because the current problem is a focused duplicate therapy clarification after a recent CMR

  • A. CMR because duplicate therapy can affect the entire medication list: Tempting because duplicate therapy is clinically significant and can reflect system-level medication list errors, but incorrect because the current issue is one focused alert in a patient who had a recent CMR. The single clue is "had a CMR 6 weeks ago." Sources: APhA/NACDS; managed care MTM workflow literature.
  • B. TMR because the current problem is a focused duplicate therapy clarification after a recent CMR: Tempting because it aligns with a dashboard trigger, and correct because targeted review is designed for exactly this kind of single issue. The discriminating clue is the isolated outside fill for omeprazole. Sources: APhA/NACDS; ASHP ambulatory care practice standards.
  • C. No review because GI therapy is outside MTM scope: Tempting if one equates scope with disease diagnosis only, but incorrect because verifying duplicative medication use and counseling on regimen safety are core pharmacist activities. The eliminating clue is a medication-related problem rather than a need for diagnosis. Sources: ACCP; APhA/NACDS.
  • D. Emergency referral because duplicate PPI use is inherently emergent: Tempting because duplication can be harmful, but incorrect because this does not automatically require emergency care in the absence of red-flag symptoms. The discriminating clue is routine clarification request, not acute toxicity. Sources: Lexicomp; APhA/NACDS.
If you missed this: Review 1.1.2.3 Application in real MTM workflow: transitions, quality flags, and follow-up sequencing — focus on quality-dashboard alerts as common TMR triggers.

8. Correct answer: B. Address the urgent discrepancy immediately, document focused intervention, and determine whether broader follow-up or CMR is needed

  • A. Continue the planned TMR only and ignore the cardiac issue because it was outside the original trigger: Tempting because pharmacists may want to stay narrowly on script, but incorrect because the new lisinopril plus sacubitril/valsartan discrepancy creates a higher-priority safety issue that cannot be ignored. The single discriminating clue is unsafe current medication confusion. Sources: ASHP transitions-of-care; APhA/NACDS.
  • B. Address the urgent discrepancy immediately, document focused intervention, and determine whether broader follow-up or CMR is needed: Tempting because it seems more complex than the original outreach, and correct because the immediate pharmacist role is focused safety clarification followed by reassessment of whether broader review is needed. The discriminating clue is restart of an old conflicting cardiac medication. Sources: ASHP transitions-of-care guidance; APhA/NACDS.
  • C. Perform no intervention until the next annual CMR because one is already on file: Tempting because timing rules can over-anchor learners, but incorrect because urgent safety issues supersede annual scheduling logic. The eliminating clue is dangerous medication discrepancy now. Sources: APhA/NACDS; pharmacist scope guardrails.
  • D. Independently discontinue lisinopril in the record without clarifying with the patient or prescriber: Tempting because the interaction concern is real, but incorrect because autonomous therapy discontinuation may exceed authority when not stated. The pharmacist should clarify, counsel, communicate, and escalate per local protocol. The eliminating clue is absence of explicit prescriptive authority. Sources: pharmacist scope guardrails; ASHP; APhA/NACDS.
If you missed this: Review 1.1.2.5 Integration: common boundary cases and how to choose safely on exam day — focus on the rule that a TMR can uncover a more urgent issue requiring immediate focused action and possible later expansion to CMR.

References

  • American Pharmacists Association and National Association of Chain Drug Stores Foundation. Medication Therapy Management in Pharmacy Practice: Core Elements of an MTM Service Model. Washington: APhA and NACDS Foundation.
  • DiPiro, Joseph T., et al. Pharmacotherapy: A Pathophysiologic Approach. McGraw-Hill.
  • American Society of Health-System Pharmacists. ASHP Guidelines on Pharmacist-Conducted Patient Education and Counseling and related ambulatory care and transitions-of-care guidance.
  • Lexicomp Online. Wolters Kluwer Clinical Drug Information.
  • Clinical Pharmacology. Elsevier.

Last reviewed: March 11, 2026

Keep reading, free

Enter your email to read lesson 2 now.

Free. We may also email you about our programs. No spam, and you can ask us to remove your email at any time.

Liked it?

BCMTMS Prep Course (BCMTMS) has 70 lessons.

PharmExPrep
Programs
For organizations
ContactLog inGet a free guide